The Madness of Vaccinating Those With Natural Immunity

Marc Girardot via: BizNews

A British friend, recovered from COVID, decided to get vaccinated despite being naturally immune. This is the email he recently sent me:

“Marc, I suffered a mild stroke on Wednesday 8 days after taking the Astrazeneca 2nd dose. Since I am a marathon runner I am a very ‘rare case’. I don’t smoke, have high blood pressure, high cholesterol, family history or come into any of the risk categories for blood clots…

You did warn me against taking the second dose and I wish I’d heeded your advice. I’ve taken a totally unnecessary risk with my life and I bitterly regret doing it.”

Contrary to most, Tony was informed; he had been told about the power of natural immunity, about the long – if not lifelong – duration of immunity, of the risk inherent to any medical procedure (yes, vaccination is a medical procedure!), as well as of the rising levels of adverse events. He admitted he hadn’t imagined it could happen to him…

Though it is hard to assess precisely the actual severity and breadth of vaccine-related adverse events, it is very clear that vaccination against COVID-19 isn’t as harmless as pharmaceuticals, mainstream media, academia, health authorities and the medical community have been saying. And, in contrast to high-risk individuals who are still susceptible, recovered people have no real benefit to balance the additional risks of vaccination.

For over a year, mainstream media, health authorities as well as many “experts” have been downplaying the power of the immune system, dismissing natural immunity and proclaiming that immunity to COVID-19 was short-lived. Simultaneously, vaccines have been portrayed as the silver bullet to this crisis, an incidental procedure with no risk whatsoever. The data shows a different picture and many are coming forward, to challenge the official narrative. We will demonstrate that this narrative is a fallacy.

The human immune system is one of the most sophisticated achievements of evolution. The survival of our species has depended on it for millenia. And today, we are still very much relying on it. For the record, 99% of people infected with SARS-CoV-2 recover without treatment. Only 1% of SARS-CoV-2 patients, who did not receive early home-based treatment, end up hospitalised. In other words, the immune system overwhelmingly protects. Even vaccines depend entirely on the immune system: vaccines essentially teach our immune systems what viral markers to be prepared for, they are not cures per se. Without a functional immune system, there can be no effective vaccine.

On the waning immunity fallacy

Once recovered, the immune response recedes, notably via a decrease in antibodies. It is not only natural; it is indispensable to restore the body to a normal balanced state. Just as a permanent state of fever would be harmful, a high number of targetless antibodies or T-cells constantly circulating throughout the body could create serious complications such as autoimmune diseases. Taking an evolutionary perspective, only those whose antibody and T-cells count waned post-infection survived. So, a dropping number of antibodies and T-cells is reassuring, even healthy.

But this decrease in T-cells and antibodies doesn’t mean at all that immunity is gone. It means the immune system has adapted to the new situation, and is now just on sentinel mode: Memory B- and T-cells, circulating in the blood and resident in tissues, act as vigilant and effective sentinels for decades:

Indeed, all recent studies show the specific anti-SARS-CoV-2 immunity remains effective – possibly for a lifetime. Our immune system is a modular platform, it can combine in an infinite number of ways to address a multitude of threats in a variety of contexts. As such, it is neutral to the viral threats it faces. In other words, there is absolutely no reason to believe that those recovered from Covid-19 would lose their immunity over the years, or even the decades to come.

On the reinfection fallacy

You might have also heard of people becoming reinfected by SARS-CoV-2. Indeed, immunity, natural or vaccine-induced, isn’t the impenetrable shield described by many. Essentially harmless and asymptomatic reinfections do take place. That is, in fact, the very mechanism by which adaptive immunity is triggered.

However, symptomatic reinfections are very rare. Like an army which adapts its response to the size and the progression of its enemy forces, adaptive immunity provides a specific, rapid and resource-optimised response. As such, reinfections are mostly asymptomatic and recovered patients are protected from severe disease.

In fact, innocuous reinfections can play a positive public health role as continuous immune updates of the population. They can help a seamless and progressive adaptation to emerging new variants and strains. And indeed a recent study showed that couples with children were more frequently asymptomatic than couples without, most likely because children acted as natural and harmless immunisation vehicles. The likely reason high density [East Asian] countries all have very low death tolls is that they have asymptomatic reinfections that regularly and widely update the immunity of the population.

On the variant fallacy

As demonstrated by the low numbers of reinfections mentioned above, but also by multiple studies, so far variants have not escaped acquired immunity. Just as Americans can speak and interact seamlessly in England, unhindered by a few word variants, natural or vaccine-induced immunity is unhindered by variants, possibly more so than vaccine-induced immunity. There is ample evidence of the sophistication and breadth of the human immune system, and it is clear that its arsenal cannot be evaded by a few minor changes in the genes of the virus.

Across the world (countries: Canada, Ecuador, Gabon, Germany, India, Singapore, Sweden, UK, USA, Tanzania, Zambia), multiple studies demonstrate high-levels of pre-existing cross-reactive T-cells and antibodies to SARS-CoV-2. In other words, many were already largely immune via other coronaviruses. This is the likely explanation for the unexpectedly high level of asymptomatics during the pandemic. More importantly, this demonstrates that even with large genetic differences, prior immunity to related coronaviruses is sufficient to avoid severe Covid. Therefore, it is quite evident [that] variants are not a concern for the general population who have already recovered.

On the vaccine better-than-the-natural-immunity fallacy

You might have heard people stating that vaccines provide better protection than natural immunity. That’s an interesting way of bending reality. How can a vaccine be more effective at immunisation than the disease it is trying to mimic?

Theoretically, there are several reasons explaining why natural immunity is better than vaccine-induced immunity:

  • Fewer immune targets: mRNA/DNA vaccines present only a fraction of the virus genetic code (5-10%). For example, they don’t utilise ORF1 highly immunogenic epitopes. Therefore, the immune system will recruit a smaller number of T-cells tapping into a narrower repertoire, consequently with a less effective response. The logic: Imagine you lose a number of key players for a football tournament – you might still win, but it will be harder.
  • Longer immune trigger time: The smaller number of epitope targets also means that the alarm to the immune system will be delayed. This is a key driver of success in the COVID-19 battle. The wider the target repertoire, the faster the encounter between dendritic cells and identifiable antigens. The logic: Like a party you go to, you can start partying much faster when you have ten friends there than when you have only one. They are just easier to find.
  • Inappropriate delivery location: The intramuscular delivery of current vaccines unfortunately doesn’t mimic viral penetration and propagation at all. Coronaviruses don’t enter the body via muscles. They do so via the respiratory tract, often infecting cell to cell. Contrary to muscle-delivered vaccines, natural immunity places a strong sentinel force of memory resident cells at the portals of entry and shuts the body entrance to the virus preemptively. From an evolutionary standpoint, this makes perfect sense. The logic: It’s much easier to stop an army coming through a narrow gorge than on the beaches of Normandy.

Recent research confirms this logic. One comparative study in Israel found the protection from severe disease to be 96·4% for Covid-19 recovered individuals but 94.4% for vaccinated ones, and concluded “Our results question the need to vaccinate previously-infected individuals.” Another reference comparative study by a team at New York University highlighted a faster, wider and more impactful humoral and cytotoxic reaction in recovered immunity versus vaccine-induced.

There is ample evidence that vaccinating people recovered from COVID doesn’t bring any benefit. It quite possibly does the opposite, because of the risk of building tolerance to elements of the virus translating into reduced immune potency.

On the vaccine innocuity fallacy

Without denigrating the incredible contribution of vaccines to modern medicine and public health, one needs to acknowledge that vaccines are a medical procedure. As such, vaccines should never be considered lightly. They are neither neutral, nor trivial, all the more so when they are injected into billions of people.

In their very nature, vaccines tinker with the sophisticated balance of one’s immune system. That in itself demands respecting rigid safety protocols. Though we have made considerable progress in our understanding of immunology, we are still very far from understanding its intricacies and subtleties, especially when it comes to novel mRNA and DNA technologies.

Because of the risk of anaphylactic shock, auto-immune diseases, unforeseen interactions, design flaws, deficient quality protocols, over-dosage, and so on – vaccines have traditionally been strictly regulated.

History teaches us to be watchful with vaccines, from the botched inactivation of polio vaccines that ended infecting 40,000 kids with polio in 1955, to the 1976 swine flu vaccine which caused 450 to develop Guillain-Barré syndrome, to the more recent vaccine-induced outbreak of polio in Sudan. The recent rejection by Brazilian health authorities of the Barhat’s Covaxin is a clear reminder of how rigorous and independent our health authorities need to be if vaccines are to promote, not hinder, public health.

After 6 months of vaccination and a year of research, a number of red signals should be alerting the would-be vaccinated and health authorities:

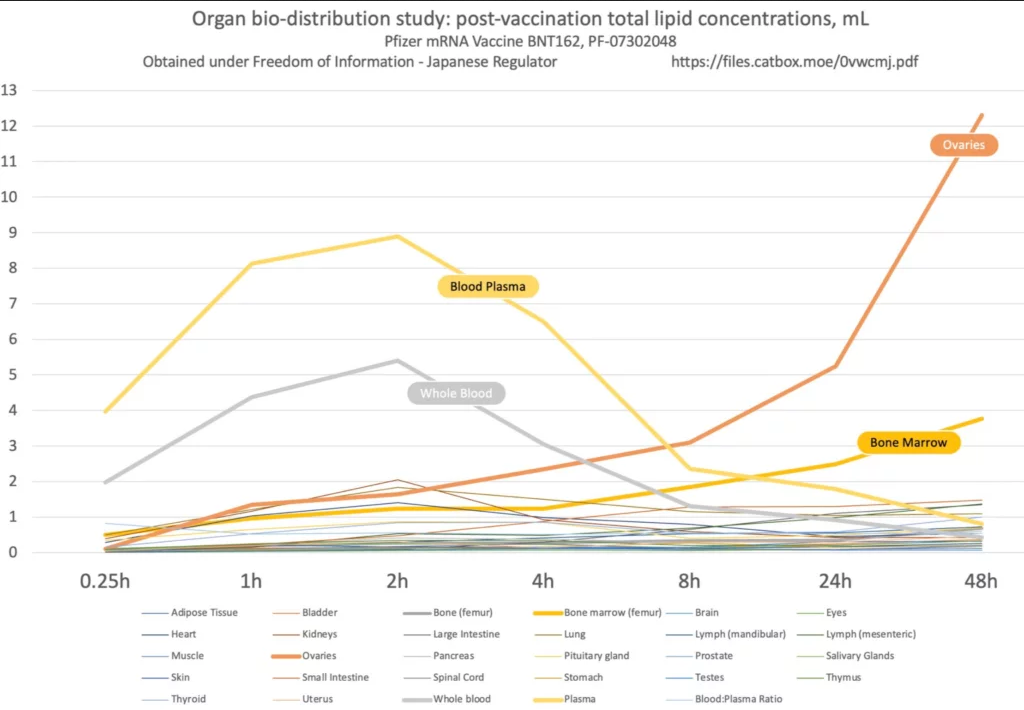
  1. Wandering nanoparticles: The lipid nanoparticles, the carriers of the mRNA, were supposed to remain in the muscle, but ended up broadly distributed throughout the body, notably in the ovaries, the liver and possibly the bone marrow.
  2. Anaphylactic PEG: A number of concerns had been raised regarding the novel use of PEG adjuvant. Notably, prior research had raised the risk of cardiac anaphylaxis at second injection.
  3. Sensitive locations: ACE-2 receptors susceptible to binding to the spike protein are highly expressed in the endothelial cells of highly sensitive areas, such as the brain, the heart, the lungs, the liver and both male and female reproductive systems.
  4. Toxic circulating spikes: The spike proteins induced by mRNA/DNA vaccines have been shown to be pathogenic, and highly inflammatory, notably because of the similarity of a spike sequence to that of Staphylococcal Enterotoxin B. It has also been found to be directly causing blood clots through platelet activation. One researcher said, “Our findings show that the SARS-CoV-2 spike protein causes lung injury even without the presence of an intact virus”.
  5. BBB disruption: A recent study highlights the risk of disruption of the blood-brain barrier, a fundamental filter mechanism to protect the brain. The spike protein has also been found to cross the BBB and create inflammation in the brain.
  6. High adverse events: Even though most likely under-reported, the overall number of serious adverse events versus other traditional vaccines remains very high. The 6,000+ deaths seen [in the US] in six months exceed all the vaccine-related deaths in 30 years. This is quite disquieting, and tends to confirm the aforementioned alarms.
  7. Children more at risk: The Covid-19 vaccines seem to be more harmful to children and teens, notably with a growing number of myocarditis events. The fact that vaccine doses are not adjusted for body weight is notably a cause for concern given the discovery of circulating nanoparticles and spike toxicity.

These are essentially just the short-term effects of these novel vaccines. There is no long-term clinical data regarding the implications of these vaccines, notably regarding autoreactive antibodies (antibodies that target one’s own body creating autoimmune diseases).

To conclude, we question why anyone healthy and recovered from COVID-19 would want or be advised to take any risk – even the most remote – in getting vaccinated given that:

  • those who have recovered from COVID-19 enjoy robust immunity;
  • natural immunity duration is decades-long, probably lifelong;
  • natural immunity effectiveness is better than vaccine-induced;
  • variants are not an immunological concern, presenting no risk of immune escape;
  • vaccines are medical interventions which should never be taken lightly, especially when still experimental;
  • there is no benefit for COVID-19 recovered; and
  • COVID-19 vaccines are obviously not as safe as stated initially by the manufacturers.

Marc Girardot is a member of PANDA and Senior Advisor in Biotech & Automotive/INSEAD MBA.

Facts on Covid Hoax – A Swiss Doctor

Overview diagrams

Global Covid mortality compared to earlier pandemics

Worldwide “cases” versus deaths

Sweden: Predicted deaths vs. reality

Corona deaths: Sweden vs. New York

Corona deaths: Sweden vs. England

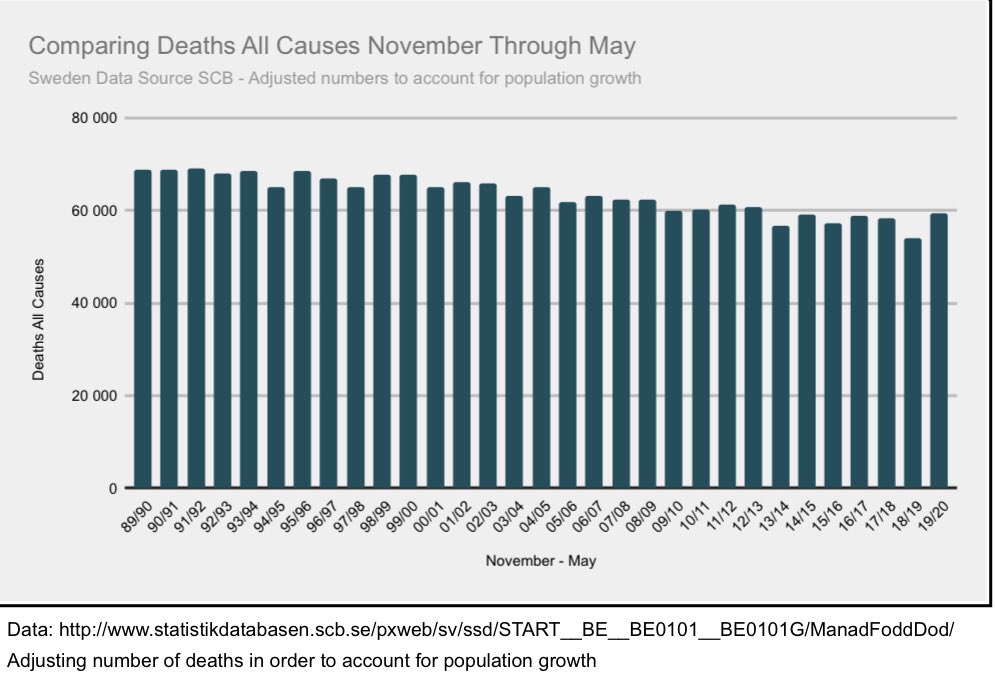
Sweden: All-cause mortality (Nov. to May) since 1990

US: Daily Covid deaths

US overall mortality 2020 vs. 2018

US: Age-adjusted death rate since 1900 (CDC)

US: Percentage of care home deaths

Percentage of care home deaths

US recessions in comparison

UK: Mortality 2020 vs. 2000

UK: Mortality 2020 (shifted) vs. 1999 and 2000

Switzerland: Mortality vs. expected value (2010-2020)

Germany: Mortality (2017 to 2020)

August 2020

A. General part
Pre-existing immunity against the new coronavirus

At the beginning of the Covid-19 pandemic, it was assumed that no immunity against the new coronavirus existed in the population. This was one of the main reasons behind the initial strategy of “flattening the curve” by introducing stay-at-home orders.

From March and April onwards, however, the first studies showed that a considerable part of the population already had a certain background immunity to the new virus, acquired through contact with earlier coronaviruses (common cold viruses). Nevertheless, it remains unclear to what extent this “background immunity” may indeed protect against the new coronavirus.

Further important studies on this topic were published in July:

· A new study from Germany came to the conclusion that up to 81% of people who have not yet had contact with the new coronavirus already have cross-reactive T-cells and thus a certain background immunity. This confirms earlier studies on T-cell immunity.

· In addition, a British study found that up to 60% of children and adolescents and about 6% of adults already have cross-reactive antibodies against the new coronavirus, which were created by contact with previous coronaviruses. This is probably another important aspect in explaining the very low rate of disease in children and adolescents.

· In the case of Singapore, a study published in the scientific journal Nature concluded that people who contracted SARS-1 in 2002/2003 still had T-cells that were reactive against the new SARS-2 coronavirus 17 years later. In addition, the researchers found cross-reactive T-cells, which were produced by contact with other, partly unknown coronaviruses, in about half of the people who had neither contracted SARS-1 nor SARS-2. The researchers suspect that the different distribution of such coronaviruses and T-cells may help explain why some countries are less affected than others by the new corona virus, regardless of the political and medical measures taken.

· Analysts have previously pointed out that many Pacific countries, and especially China’s neighbouring countries, have so far had very low Covid death rates, regardless of their population structure (young or old) and the measures taken (with or without lockdown, mass tests, masks, etc.). A possible explanation for this could be the spread of earlier coronaviruses.

· Harvard immunologist Michael Mina explained that the “drop in antibody concentration” after Covid disease, dramatized by some media, was “perfectly normal” and “textbook”. The body ensures long-term immunity through T-cells and memory cells in the bone marrow, which can quickly produce new antibodies when needed.

See also: Immunological studies on the new coronavirus

Other medical updates

Wuhan: A Harvard modelling study in the scientific journal Nature came to the conclusion that even in the Covid epicentre Wuhan, up to 87% of the infections went unnoticed, i.e. remained without symptoms or mild. This means that the Covid19 lethality (IFR) in Wuhan may also fall to about 0.1% or below. The Nature study confirms an earlier Japanese study in the journal BMC Medicine, which calculated an IFR of 0.12% for Wuhan already back in March.

However, Chinese authorities couldn’t yet know this comparatively low lethality in January and February and therefore built additional clinics at short notice, many of which eventually remained mostly unused. Only the systematic test results from South Korea and the cruise ship Diamond Princess showed that the lethality of the new corona virus in the general population is indeed lower than initially feared.

Italy: The Italian health authority ISS published a new analysis of the cause of death in about 5000 corona patients. According to this analysis, Covid was the direct cause of death in 89% of the cases. In 11%, other diseases such as heart problems, cancer or dementia were the primary cause of death. Covid was the sole cause of death in 28% of cases. It is also known that in about 4% of the deaths, no medical preconditions were present.

Covid lethality: In May, the US health authority CDC published a cautious “best estimate” of covid lethality (IFR) of 0.26% (assuming 35% asymptomatic infections). In July, a new IFR of 0.65% was published. However, this new value is not based on own calculations or new studies, but on a meta-study in which the existing literature was simply searched for all previous IFR values.

Thus, the meta-study mainly consists of previous modelling studies as well as “raw IFR values”, which are much too high compared to the actual, population-based IFR values from antibody studies. With few exceptions, the real IFR values are between 0.1% and 0.4%, and when mucosal and cellular immunity are taken into account, they are approximately 0.1% or less.

However, the virus has spread much faster than anticipated, thus causing a temporarily high death rate in some places, especially if nursing homes and hospitals got affected.

Non-infectious virus fragments: The U.S. CDC points out that in most Covid patients, infectious virus particles are no longer detectable ten to fifteen days after the first symptoms. However, non-infectious virus fragments (RNA) can still be found up to three months after the first symptoms. This is likely to be a significant problem with regard to PCR tests, as many people who have long since ceased to be infectious still test positive, triggering far-reaching tracing and quarantine false-alarms.

Deaths with or by or without coronavirus: In England and some other countries it has been reported that all deceased persons who tested positive for the new coronavirus since the beginning of the year were counted as Covid deaths – regardless of the time of the test, a possible recovery, and the actual cause of death. In the US state of Colorado, it was found that about 10% of deaths were with but not from coronavirus. In other US states, further cases of “corona deaths” became known that in reality were test-positive homicide victims and motorcycle accidents.

Children and schools

It has been known since March that the risk of disease and transmission in children is minimal in the case of Covid19. The main reason for this is probably a pre-existing immunity due to frequent contact with previous coronaviruses (i.e. cold viruses). There was and is therefore no medical reason for the closure of primary schools, kindergartens and day-care centres and for special protective measures in schools.

In the meantime, further studies on this issue have been published:

· The British epidemiologist Professor Mark Woolhouse stated that there is not a single confirmed case of infection of a teacher by a pupil worldwide.

· Tracing pioneer Iceland found “not a single case where a child under 10 infected their parents.”

· US CDC director Robert Redfield explained that additional deaths from suicides and drug overdoses by adolescents have been “far greater” than Covid deaths in recent months.

· A joint report from Sweden (without primary school closure) and Finland (with primary school closure) concluded that there was no difference in infection rates among children in the two countries.

· In the USA, three times more children up to 14 years of age have died of influenza than of Covid-19 (101 versus 31) since the beginning of the year, according to the CDC.

· A Canadian study found that most of the children with “Kawasaki-like” inflammatory symptoms had no corona infection at all. The disease in children is “very, very rare”, the researchers said.

· A German study came to the conclusion that children act epidemiologically “like brake blocks” and slow down the spread of the new corona virus.

Critical expert opinions

· The German virologist Hendrik Streeck advocates a pragmatic approach to the new coronavirus and targeted measures for people at high risk. According to Streeck, the long-term suppression of the virus and the hope for a possible vaccine are not sensible strategies.

· Professor Carl Heneghan, Director of the Oxford Centre for Evidence-Based Medicine, explains in an interview that there is still no evidence for the effectiveness of masks in the general population. A permanent suppression strategy like the one in New Zealand is not sensible and causes high damage in the long term. The lethality (IFR) of Covid-19 is about 0.1% to 0.3% and is thus comparable to previous flu epidemics and pandemics.

· The Swedish chief epidemiologist Anders Tegnell explains in an interview that eradication of the virus is not an option. In Sweden, the infections slowed down considerably even without a lockdown, and daily deaths now are close to zero. The evidence for the benefit of masks is still “very weak” and they might even be counterproductive. An introduction of masks at this point in time would make no sense. The lethality of Covid-19 is between 0.1% and 0.5% and does not “radically differ” from influenza.

· The epidemiologist and systems biologist Professor Francois Balloux, Director of the British UCL Genetics Institute, explains in an article that Covid-19 is comparable to a pandemic (but not seasonal) influenza. The main difference is the age-risk distribution: while Covid-19 is mainly dangerous for older people, a pandemic influenza is also life-threatening for younger people and children. Professor Balloux points out that the “Russian influenza pandemic” of 1889 may have been triggered by the coronavirus OC-43, which is now considered one of the four typical cold viruses.

· The Swiss chief physician for infectiology, Dr. Pietro Vernazza, pleads for a “controlled natural immunization” of society as an alternative to the “eradication strategy”. In most cases, Covid-19 is mild and the actual mortality rate is about 0.1%, which is in the range of a severe influenza. The Swedes “did nothing wrong” with their strategy, according to Vernazza.

· The former director of the Institute of Immunology at the University of Bern, Professor Beda Stadler, also pleads for a controlled spread of the virus. The danger of the virus had been overestimated due to the false assumption of a lack of immunity. Professor Stadler is critical of compulsory masks and mass tests. Stadler, who is now emeritus, explains that many younger immunologists no longer dare to speak out publicly on the subject due to the extreme polarisation of the debate by politics and the media.

On the other hand, Professor Karin Mölling, the former head of the Department of Virology at the University of Zurich and one of the earliest critical voices on corona measures, has now partly changed her opinion: Due to the sometimes serious lung damage, the virus should not be underestimated and containment measures are important.

The clinical picture of Covid-19

The lower-than-expected lethality of Covid-19 should not hide the fact that the new coronavirus, due to its efficient use of the human ACE2 cell receptor, in some cases can lead to severe disease with complications in the lung, the vascular and nervous systems and other organs, some of which can persist for months.

While it is true that most of these symptoms can also occur in severe influenza (including thrombosis, heart muscle inflammation, and the temporary loss of the sense of smell), they are indeed more frequent and more pronounced in the novel Covid-19 disease.

In addition, even apparently “mild” disease (without hospitalization) can in some cases lead to protracted complications with breathing problems, fatigue or other symptoms. The US CDC came to the conclusion that after one month, about one third of the “mild” cases still showed such symptoms. Even in the 18 to 34-year-olds without preconditions, about 20% still had after-effects.

On the positive side, researchers at a German clinic recently reported good chances of recovery: “We can see that the lungs can heal well, even in patients who have had three weeks of intensive care”. After three months, 20% of the intensive care patients had healthy lungs again, and in the remaining patients a clear regeneration was visible.

Nevertheless, the primary goal should be to avoid a progression of the disease.

On the treatment of Covid-19

Note: Patients are asked to consult a doctor.

Many countries adopted the strategy of imposing a lockdown during or after a wave of infection, thereby locking already infected high-risk individuals in their homes without treatment until they developed severe breathing problems and needed intensive care treatment immediately. Even today, test-positive high-risk persons are often simply quarantined without treatment.

This is not an ideal approach. Numerous studies and doctors’ reports have now shown that for people at high risk or with high exposure, early treatment immediately on onset of the first typical symptoms is crucial to avoid disease progression and hospitalization.

Studies and medical reports from various countries in Asia and the West recommend a combination protocol of zinc (which inhibits the RNA replication of coronaviruses), the antimalarial agent HCQ (which promotes the cellular uptake of zinc and has other anti-viral properties), and, if necessary, an antibiotic (to prevent bacterial superinfections) and a blood thinner (to prevent thrombosis and lung embolism).

Yale professor and physician Harvey A. Risch argues in a recent commentary that early treatment with HCQ and zinc as well as an antibiotic has proven to be “highly effective”. In the USA alone, according to Professor Risch, 70,000 to 100,000 deaths could have been prevented by the systematic use of HCQ. Risch is therefore calling for an immediate and prescription-free release of this medication, as is already the case in many other countries.

Meanwhile, a bizarre battle has broken out in western industrialised countries over the use of low-cost HCQ, which has been used successfully and safely for decades in the prevention and treatment of malaria and several other diseases. This battle appears to be driven in part by political and commercial interests and may produce a great many casualties.

Opponents of HCQ went as far as publishing falsified studies and using lethal doses during trials, as Dr. James Todaro explains, who uncovered one of these frauds that fooled top science journals, the WHO and health experts worldwide.

Many of these anti-HCQ activities are connected to pharmaceutical company Gilead, which wants to sell a drug that is over a hundred times more expensive (Remdesivir), but which is only used on intensive care patients and has some severe side effects.

In addition, a potentially effective early treatment stands in the way of the billion-dollar global vaccination strategy being pursued by numerous governments, pharmaceutical companies and vaccine investor Bill Gates. Directors of vaccine companies have already made about one billion dollars with stock and option gains alone, even without yet delivering a vaccine.

The hope for a safe and effective vaccine, however, remains questionable: Contrary to the positive media presentation, in the second test round of the RNA vaccine from the US company Moderna, 80% of the volunteers in the medium and high-dose groups (average age 33 years and healthy) reacted with moderate to severe side effects.

Read more: On the treatment of Covid-19

Bill Gates on vaccine side effects (CBS, July 23, 2020)

The effectiveness of face masks

Various countries are discussing or have already introduced mandatory face masks in the general population. In the updates of June and July, however, it was shown that the evidence for the effectiveness of cloth masks in the general population is still rather weak, contrary to what is reported in many media.

In previous influenza pandemics, cloth masks had no influence on the occurrence of infection. Despite masks, Japan had its last flu epidemic with more than five million diseased just one year ago, in January and February 2019. Even the outbreak of the Covid pandemic in Wuhan could not be stopped by the widespread use of masks there.

Due to the significantly lower hospitalisation and mortality rates of Covid-19 (compared to the original assumptions), masks are not necessarily required to “flatten the curve”. Masking only makes sense – if at all – in the context of a vaccination strategy that aims to suppress the virus until a vaccine is available.

BBC medical correspondent Deborah Cohen explained in mid-July that the partial update of the WHO recommendation on masks was due not to new evidence but “political lobbying”: “We had been told by various sources WHO committee reviewing the evidence had not backed masks but they recommended them due to political lobbying. This point was put to WHO who did not deny.”

The “political lobbying” is likely referring to the group “Masks for All”, which was founded by a “Young Leader” of the Davos forum and which is lobbying authorities and governments for a worldwide face mask obligation.

In connection with masks, the question also arises as to whether the new coronavirus can be transmitted over large areas by aerosols. According to experts, true aerosol transmission even outdoors still seems unlikely – otherwise the spread of the virus would have a different dynamic and, contrary to reality, would often be untraceable.

However, an aerosol-like transmission indoors – especially with closed air circulation by fans or during intensive activities such as singing and dancing – seems increasingly probable or certain due to various incidents.

In the case of aerosol transmission, however, cloth masks are likely to offer even less protection than against droplets due to their pore size and inaccurate fit. This was demonstrated, for example, by the corona outbreak at the German meat processor Toennies, which occurred at an air-conditioned workplace over a distance of up to eight metres despite the requirement to wear masks.

On the question of “asymptomatic transmission”, it can currently be said that true asymptomatic transmission still seems to be rare (which may explain the very low transmission rate in children), whereas pre-symptomatic transmission in the days before the first symptoms appear (with already high virus load) is very likely and may explain the rapid spread of the virus.

Pre-symptomatic transmission is also known from influenza, but the incubation period of influenza is much shorter, so this may be somewhat less relevant.

The following expert reviews and articles critically examine the effectiveness of cloth masks in the general population:

· Profs. Tom Jefferson and Carl Heneghan (Oxford): Masking lack of evidence with politics

· Dr. Lisa Brosseau and Dr. Margaret Sietsema, Center for Infectious Disease Research and Policy, University of Minnesota: Masks-for-all for COVID-19 not based on sound data

· Professor Michael T. Osterholm, Center for Infectious Disease Research and Policy, University of Minnesota: My views on cloth face coverings for the public for preventing COVID-19

· Naoya Kon: Cloth face masks offer zero shield against virus, a study shows

· Eliza McGraw: Everyone wore masks during the 1918 flu pandemic. They were useless.

The Swedish chief epidemiologist Anders Tegnell recently stated that the introduction of masks at this point in time, and even in public transport, would be “pointless” in view of the rapidly decreasing number of cases in Sweden. The Dutch government has stated that it will not in general recommend masks because the scientific evidence for their effectiveness is weak.

On the other hand, face masks are not harmless, as the following evidence shows:

· The WHO warns of various “side effects” such as difficulty breathing and skin rashes.

· Tests conducted by the University Hospital of Leipzig have shown that face masks significantly reduce the resilience and performance of healthy persons.

· A German psychological study with about 1000 participants found “severe psychosocial consequences” due to the introduction of mandatory face masks in Germany.

· The Hamburg Environmental Institute warned against the inhalation of chlorine compounds in polyester masks as well as problems in connection with disposal.

· The European rapid alert system RAPEX has already recalled 70 mask models because they did not meet EU quality standards and could lead to “serious risks”.

· In China, two boys who had to wear a mask during sports classes fainted and died.

· In the US, a car driver wearing an N95 (FFP2) mask fainted and crashed into a pole.

Conclusion: It is still possible that cloth masks can slow down the rate of infection in the general population, but the evidence for this is currently limited and the potential benefits are mainly relevant in the context of a long-term and still uncertain vaccination strategy.

Read more: Are face masks effective? The evidence.

Is Covid-19 a pure “test epidemic”? Certainly not.

Some particularly skeptical observers still seem to perceive Covid-19 mainly or solely as a “test epidemic”. However, this position has been untenable for months already.

The best known “test epidemic” is the so-called swine flu of 2009/2010, a rather mild influenza virus that only caused worldwide anxiety due to mass testing and media panic. A commission of the Council of Europe later called the swine flu a “fake pandemic” and a “big pharma fraud”.

What was noteworthy at the time was that a few months earlier, the WHO changed its pandemic guidelines and removed the criterion of increased lethality. In addition, pharmaceutical companies signed secret contracts worth billions with governments for a vaccine that later led to sometimes serious neurological damage and had to be disposed of for the most part.

Finally, researchers discovered that the swine flu virus itself probably originated from vaccine research and was released through a leak (or worse).

On the other hand, due to its special characteristics – in particular the very efficient use of the ACE2 cell receptor – the new coronavirus is a rather dangerous and easily transmissible SARS virus which can cause severe damage to the lungs, blood vessels and other organs. The good fortune is that many people already have a certain immunity to the new virus or at least are able to neutralize it on the mucosal membrane.

Covid-19 is therefore a real and serious pandemic and comparable to the (still stronger) flu pandemics of 1957/58 (Asian flu) and 1968 to 1970 (Hong Kong flu). The comparison with the swine flu of 2009 is only possible because the deaths caused by swine flu were greatly exaggerated.

(On the other hand, it should be remembered that during the 1968/1970 flu pandemic – or rather in the summer between the two main waves – the famous Woodstock festival was held and social life mostly went on as usual).

However, it can be argued that the real Covid19 pandemic has been amplified by a “test pandemic” due to mass testing in the general population, causing additional panic and high costs.

Stanford Professor Scott Atlas argued already in May that mass testing in the general population is of little use and that testing should instead be limited to vulnerable institutions such as nursing homes and hospitals (including for visitors).

Daily mass testing is also not effective because, according to antibody studies, the virus is already much more widespread than PCR tests show, anyway. Moreover, the tests are susceptible to false-positive (and false-negative) results and non-infectious virus fragments.

Countries such as Japan, Sweden and Belarus have shown that the pandemic can be controlled without a lockdown and without mass testing – and in the case of Sweden and Belarus also without masks – as long as the sensitive facilities are protected.

Conclusion: Covid-19 is a real and serious pandemic comparable to the (still stronger) influenza pandemics of 1957 and 1968, but in addition to the real Covid-19 pandemic, there is indeed a “test pandemic” that causes unnecessary panic and high costs.

Covid-19: real pandemic and test pandemic

The origin of the new coronavirus

The origin of the new SARS coronavirus remains unclear. However, researchers with access to Chinese documents were able to show in May that the closest related coronavirus was found in a mine in southwest China, where six miners contracted Covid-like pneumonia in 2012 and three of them died.

The miners’ illness was clinically virtually identical to today’s (severe) Covid-19, which is why some analysts have proposed to call the disease Covid-12 instead of Covid-19.

The Virological Institute in Wuhan received virus samples from the mine as well as from the tissue of the deceased miners in 2012 and 2013. It is conceivable that this virus escaped from the laboratory in autumn 2019.

In addition to the Chinese institute, however, the US health authority CDC and the US Department of Defense have also been shown to be working with SARS-like viruses from bats. The US NGO “Eco Health Alliance” cooperated on this issue with both the US Pentagon and the Virological Institute in Wuhan.

Direct transmission by an animal is also still conceivable, although previous candidates such as the well-known animal market in Wuhan or the Pangolin theory have been ruled out by experts in the meantime.

Read more: Origin of Covid-19 Virus: The Mojiang Miner Hypothesis

B. Countries and regions
USA

The USA is one of the countries most affected by the new coronavirus so far. This could have political and medical reasons.

Medically, there are many relevant pre-existing conditions in the US population, such as obesity, heart problems and diabetes. Air conditioning systems could promote aerosol-like transmission indoors. Politically, there have been serious mistakes in dealing with nursing homes, misplaced incentives in the treatment of patients, and problematic back-and-forth with lockdowns.

· The US already has over 150,000 corona deaths, putting it in the range of a pandemic influenza, comparable to the 1957 and 1968 pandemics.

· 45% of corona deaths occurred in nursing homes. Over 50% of all deaths occurred in the six states that actively placed Covid patients in nursing homes.

· For people of school and work age (up to 65), corona mortality is comparable to mortality from other pneumonia diseases (e.g. influenza), according to the CDC. For children and adolescents, Covid is three times less dangerous than influenza.

· A nationwide antibody study showed that the new coronavirus is 6 to 24 times more widespread than assumed on the basis of PCR tests, depending on the region. However, the antibody levels are still in the single-digit percentage range in most regions, indicating that exposure to the coronavirus is less much less than 50% in many places.

· While the number of daily positive tests reached a peak in mid-July due to the high number of tests, the number of daily deaths was only half as high as in April, although recently with a slight upward trend again (see graph below).

· In Florida there were reports of at times allegedly very high positivity rates. However, an analysis showed that various laboratories only reported the number of positive tests and thus an apparent positivity rate of 100%. The actual positivity rate in Florida was mostly in the single-digit percentage range. In terms of deaths per capita, Florida remains in the lower midfield compared to the other states.

· The median age of Covid deaths in the USA is 78.5 years. This is higher than the median age of “other deaths”, but lower than the median age of Covid deaths in Europe (80 to 86).

· Yale professor and epidemiologist Harvey A. Risch recently called for immediate over-the-counter availability of HCQ for the early treatment of Covid disease.

· A group of doctors calling itself “America’s Frontline Doctors” held a press conference with the same goal of making HCQ available. The video of the press conference was seen by 20 million people within a day before it was deleted by Facebook & Co. as “misinformation”.

US: Age-adjusted death rate since 1900 (CDC)

US: Daily Covid deaths

Covid deaths: New York vs. Florida (Paul Yowell)

US: Percentage of care home deaths

Great Britain

· In England and Wales there have been about 50,000 corona deaths so far. The overall mortality rate is thus still about 10,000 deaths below the strong flu epidemic of 1999/2000.

· There has been no excess mortality among those under 45 years of age compared to the last five years.

· The cumulative corona deaths since March correspond almost exactly to the cumulative influenza and pneumonia deaths since the start of the winter season in December 2019.

· Since mid-June, England and Wales have been in relative under-mortality and daily corona deaths have been below daily influenza and pneumonia deaths since then.

· By mid-April, 45% of NHS nursing staff had already been infected with corona. A significant proportion of patients may have been infected with corona in hospital. Corona patients were also transferred to nursing homes in England, which led to additional deaths.

England: Deaths in 2020 versus 2000 (InProportion)

France

France was relatively hard hit by the corona pandemic and registered about 30,000 corona deaths by the end of May according to the health authority SPF. About 50% of these deaths occurred in nursing homes, the average age of the deaths is 81.3 years. The median age of intensive care patients was about 67 years.

The region around Paris, eastern France and northern France were particularly hard hit, while large parts of western France and southwestern France were hardly affected at all (so far).

So although only part of France was affected by Covid, the cumulative excess mortality since the beginning of the year (compared to the baseline) is about 50% higher than during the seasonal flu waves of the past five years. In Greater Paris, the excess mortality rate is even around 500% or 10,000 people higher than in previous years (see graphs below).

Covid deaths accounted for around 16% of all deaths nationwide, but in Greater Paris, the figure was almost 40% of all deaths from early March to late May. The weekly peak mortality due to Covid-19 is comparable to the record hot summer of 2003 (see graph below).

Didier Raoult, a well-known professor of medicine and HCQ pioneer from Marseille, criticized the lack of early treatment and the ban on HCQ at a parliamentary hearing at the end of June. Until 2019, HCQ was available in France without prescription. At the beginning of the pandemic, however, its use was restricted to clinics and eventually banned altogether. The reason for the ban was the falsified Lancet study from the end of May (which was later retracted).

In his clinic, Prof. Raoult had been able to reduce the case fatality rate to a very low 0.9% by early treatment with HCQ, according to a published retrospective analysis.

France: Excess mortality 2015-2020

France: Excess mortality in Paris Region (IDF) and Eastern France, 2015-2020

France: Weekly mortality since 2003

France: Regional excess mortality, March to May 2020

Charts and report: Santé Public France

Germany

Germany counts only about 9000 corona deaths and has not experienced any significant excess mortality (in population-adjusted terms there was even a slight under-mortality).

At the end of June, however, only 1.3% of blood donors had IgG antibodies against the new coronavirus. This value is very low. Even if non-blood donors (including children and sick persons), T-cells and mucosal (IgA) immunity are taken into account, exposure of the population to the virus is hardly more than 10% to 15%.

This means that the new coronavirus has not yet spread widely in Germany. The measures or – more likely – the anticipation of the measures by the population therefore seem to have been “successful” in this sense (see graph below).

On the other hand, this means that epidemiologically, Germany is essentially still where it was in April and that the risk of a new and stronger increase in infections and disease is indeed real. The comparison with France shows what this can entail.

The German government currently seems to be following a suppression and vaccination strategy. This strategy is socially and economically costly and its success remains uncertain. As an alternative or addition, an early treatment concept should be examined.

The political corona situation in Germany remains tense. Repeatedly, sanctions have been imposed on doctors, professors, lawyers and civil servants who are critical of corona, and in some cases serious attacks occurred against skeptical journalists and activists.

Since June, an extra-parliamentary committee of inquiry consisting of lawyers and medical experts has been dealing with the German Corona government policy. It should not be forgotten, however, that the corona pandemic in Germany is probably not yet over, given that by the end of June, only 1.3% of blood donors had IgG antibodies against the virus.

Germany: Covid ICU patients and deaths plus measures and events (Source: CIDM)

Switzerland

· The Swiss annual excess mortality is currently close to zero (see graph), which is below most flu waves of the last ten years. This is due to the mild winter and the very high median age of the approximately 1700 corona deaths (84 years). About 50% of the deaths occurred in nursing homes. The effect of the lockdown remains questionable.

· In the former hotspots Ticino and Geneva, IgG antibody levels in May were about 10%, about ten times higher than found by daily PCR tests. Taking mucosal and cellular immunity into account, exposure in southern and western Switzerland could already be around 50%. In German-speaking Switzerland, however, exposure is likely to be lower. The risk of a “second wave” is therefore real.

· In principle, the Swiss government is pursuing a suppression and vaccination strategy, which it is supplementing with mass testing, contact tracing and compulsory masking. As an alternative, infectiologist Dr. Pietro Vernazza brought up the idea of controlled exposure with protection of risk groups based on the Swedish model.

· Switzerland still has no early treatment strategy and thus risks an unnecessarily high hospitalisation and death rate.

· Sweden and Belarus, both of which managed the corona pandemic without a lockdown and without compulsory masks, have been removed from the Swiss list of “high-risk countries” in mid-July. Sweden had previously put Switzerland on its own high-risk list. In fact, the increase in Swedish “cases” was solely due to an increase in tests.

· A referendum was launched against the corona tracing app “SwissCovid”. The initiators are raising data protection and security concerns. Previously, Swiss Professor Serge Vaudenay published a critical analysis of the app, which isn’t as transparent as claimed, leaving Google and Apple in control, Vaudenay said.

· A referendum is also being prepared against the Swiss “Covid-19 Law”, which extends the Corona emergency law until the end of 2022. In addition, a petition has been launched calling for an extra-parliamentary commission of inquiry into the corona measures.

· A flyer campaign against the compulsory use of masks in public transport also caused a stir. The director of the BAG hastily called the arguments of the critics “fake news”.

· Infosperber: The Covid-19 task force massively exaggerated the benefits of masks

· For more current and critical corona analyses see corona-transition.org

Switzerland: Cumulative mortality versus expectation value (2010-2020)

Sweden

· In Sweden, daily corona deaths are now close to zero. The overall mortality rate is in the range of earlier strong flu waves. Even the monthly peak mortality (in April 2020) remained below the strong flu waves of the 1990s.

· The example of Sweden (and Belarus) shows that a lockdown was not necessary if the population and institutions were well prepared. However, from the perspective of many lockdown advocates – governments and the media – this is very difficult to admit.

· Sweden is one of the few Western countries that – on the basis of the medical evidence – has not closed its primary schools. This decision was correct, too.

· Sweden made two real mistakes, which ironically are not covered by most of the media: 1) The nursing homes in the Stockholm area were protected too late and caused over 50% of Swedish deaths. 2) Sweden had no early treatment strategy that could have reduced the hospitalisation and death rates.

· Swedish cities showed an IgG antibody prevalence between 10% and 20% in July, which, together with mucosal and cellular immunity, indicates that the population was exposed between 50% and 100%. Sweden is therefore probably the best placed of all western countries to start the coming winter.

The following graphs compare the deaths in Sweden with those in England and New York.

Corona deaths: Sweden vs. England

Corona deaths: Sweden vs. New York

Charts: Paul Yowell

India

India, which relies on early treatment and even prophylaxis with the antimalarial drug HCQ, officially counts only about 35,000 corona deaths among its 1.3 billion people.

An Indian antibody study came to the conclusion that around 23% of the 20 million inhabitants of the Indian capital Delhi already have antibodies against the new corona virus. This is about 35 times more people than confirmed by PCR tests.

This means that Delhi (and some other major cities) could already be beyond or near the herd immunity threshold, taking into account mucosal and cellular immunity.

Latin America

Brazil has by now suffered 90,000 Covid deaths and thus ranges between the Netherlands and France in terms of deaths per population. In the meantime, Brazil has introduced an early treatment concept based on zinc and HCQ.

Chile and Peru currently have an even higher death rate than Brazil (based on population). With close to 20,000 deaths, Peru is in the range of Italy and Spain.

C. Political notes

· The US economy contracted by an annualized 32.9% in the second quarter, the highest rate since 1947. The second highest decline was in 1958 (10%) – in the wake of the Asian flu pandemic.

· In the US, up to 28 million people might lose their homes due to corona lockdowns and the economic downturn, which could trigger a new mortgage crisis.

· The German economy contracted by 10.1% in the second quarter compared with the same quarter of the previous year – the biggest decline since 1970.

· According to the UN, the corona lockdowns and the global economic depression could plunge up to 225 million people worldwide into a famine by the end of the year.

· The EU Commission demands or plans the “networking” of national corona tracing apps.

· The NGO Privacy International warns of a “looming disaster” with immunity passports and digital identity cards.

· The authoritarian government of Turkmenistan apparently banned the use of the word “coronavirus”. Consequently, there are no coronavirus deaths in the country, at least officially. Those who wear a mask are arrested by police, Reporters without Borders said.

July 2020

On the development of the pandemic

In most Western countries, the peak of coronavirus infections was already reached in March or April and often before the lockdown. The peak of deaths in most Western countries was in April. Since then, hospitalizations and deaths have been declining in most Western countries (see graphs below).

This development also applies to countries without a lockdown, such as Sweden, Belarus and Japan. Cumulative annual mortality in most western countries continues to be in the range of a mild (e.g. CH, AT, DE) to strong (e.g. USA, UK) influenza season.

After the end of the lockdowns, the number of corona tests in the low-risk general population has increased strongly in many countries, for example in connection with people returning to work and school.

This led to a certain increase in positive test results in some countries or regions, which was portrayed by many media and authorities as an allegedly dangerous increase in “case numbers” and sometimes led to new restrictions, even if the rate of positive tests remained very low.

“Case numbers” are, however, a misleading figure that cannot be equated with sick or infected people. A positive test can, for example, be due to non-infectious virus fragments, an asymptomatic infection, a repeated test, or a false-positive result.

Moreover, counting alleged “case numbers” is not meaningful simply because antibody tests and immunological tests have long shown that the new coronavirus is up to fifty times more widespread than assumed on the basis of daily PCR tests.

Rather, the decisive figures are the number of sick people, hospitalisations and deaths. It should be noted, however, that many hospitals are now back to normal operation and all patients, including asymptomatic patients, are additionally tested for the coronavirus. Therefore, what matters is the number of actual Covid patients in hospitals and ICUs.

In the case of Sweden, for example, the WHO had to withdraw the classification as a “risk country” after it became clear that the apparent increase in “cases” was due to an increase in testing. In fact, hospitalisations and deaths in Sweden have been declining since April.

Some countries have already been in a state of below-average mortality since May. The reason for this is that the median age of corona deaths was often higher than the average life expectancy, as up to 80% of deaths occurred in nursing homes.

In countries and regions where the spread of the coronavirus has so far been greatly reduced, it is nevertheless entirely possible that there will be a renewed increase in Covid patients. In these cases, early and effective treatment is important (see below).

Global Covid-19 mortality is currently – despite the significantly older population nowadays – a whole order of magnitude below the flu pandemics of 1957 (Asian flu) and 1968 (Hong Kong flu) and in the range of the rather mild “swine flu pandemic” of 2009.

The following charts illustrate the discrepancy between “cases” and deaths:

The following charts compare Covid mortalities to earlier flu seasons (more):

The following chart compares deaths in Sweden (no lockdown) New York State:

Deaths in Sweden versus New York State (FEE/Paul Yowell)

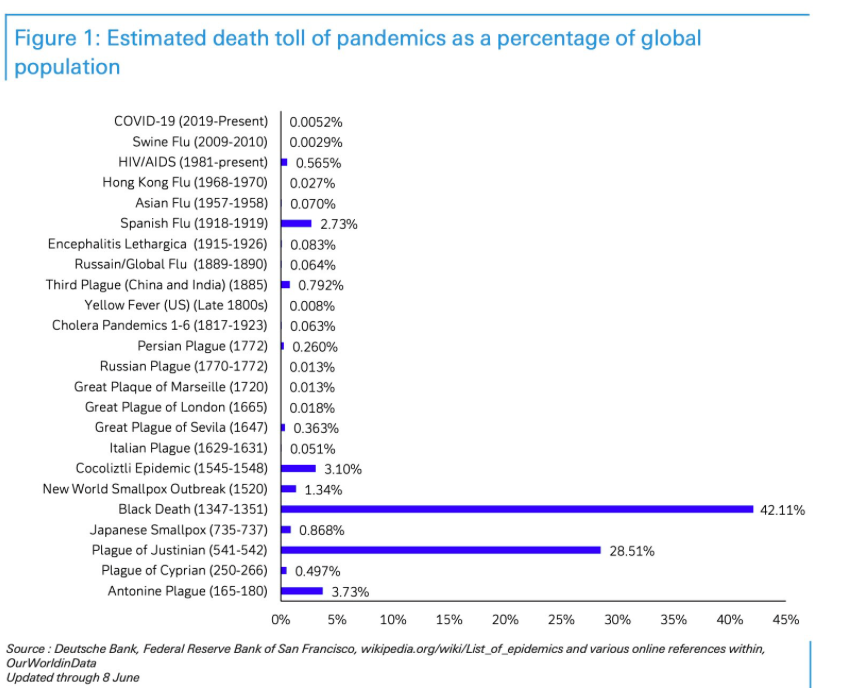
The following chart compares the Covid-19 pandemic to earlier pandemics:

Global Covid mortality compared to earlier pandemics (DB Research)

On the lethality of Covid-19

Most antibody studies have shown a population-based Infection Fatality Rate (IFR) of 0.1% to 0.3%. The US health authority CDC published in May a still cautious “best estimate” of 0.26% (based on 35% asymptomatic cases).

At the end of May, however, an immunological study by the University of Zurich was published, which for the first time showed that the usual antibody tests that measure antibodies in the blood (IgG and IgM) can detect at most about one fifth of all coronavirus infections.

The reason for this is that in most people the new coronavirus is already neutralised by antibodies on the mucous membrane (IgA) or by cellular immunity (T cells) and no symptoms or only mild symptoms develop.

This means that the new coronavirus is probably much more widespread than previously assumed and the lethality per infection is around five times lower than previously estimated. The real lethality could therefore be significantly below 0.1% and thus in the range of influenza.

At the same time, the Swiss study may explain why children usually develop no symptoms (due to frequent contact with previous corona cold viruses), and why even hotspots such as New York City found an antibody prevalence (IgG/IgM) of at most 20% – as this already corresponds to herd immunity.

The Swiss study has in the meantime been confirmed by several more studies:

1. A Swedish study showed that people with mild or asymptomatic disease often neutralized the virus with T-cells without the need to produce antibodies. Overall, T-cell immunity was about twice as common as antibody immunity.

2. A large Spanish antibody study published in Lancet showed that less than 20% of symptomatic people and about 2% of asymptomatic people had IgG antibodies.

3. A German study (preprint) showed that 81% of the people who had not yet had contact with the new corona virus already had cross-reactive T-cells and thus a certain background immunity (due to contact with previous corona cold viruses).

4. A Chinese study in the journal Nature showed that in 40% of asymptomatic persons and in 12.9% of symptomatic persons no IgG antibodies are detectable after the recovery phase.

5. Another Chinese study with almost 25,000 clinic employees in Wuhan showed that at most one fifth of the presumably infected employees had IgG antibodies (press article).

6. A small French study (preprint) showed that six of eight infected family members of Covid patients developed a temporary T-cell immunity without antibodies.

Video interview: Swedish Doctor: T-cell immunity and the truth about Covid-19 in Sweden

In this context, a US study in the journal Science Translational Medicine, using various indicators, concluded that the lethality of Covid-19 was much lower than originally assumed, but that its spread in some hotspots was up to 80 times faster than suspected, which would explain the rapid but short-duration increase in patients.

A study in the Austrian ski resort of Ischgl, one of the first European “corona hotspots”, found antibodies in 42% of the population. 85% of the infections went “unnoticed” (i.e. very mild), about 50% of the infections went completely without (noticeable) symptoms.

The high antibody value of 42% in Ischgl was due to the fact that Ischgl also tested for IgA antibodies in the blood (instead of only IgM/IgG). Additional tests for mucosal IgA and for T-cells would undoubtedly have shown even higher immunity levels close to herd immunity.

Ischgl saw two Covid-related deaths (both of them men over 80 with preconditions), resulting in a ‘crude IFR’ of 0.26%. Considering the population structure and the actual extent of immunity, the population-based Covid lethality is likely to be below 0.1%

Due to its rather low lethality, Covid-19 falls at most into level 2 of the five-level pandemic plan developed by US health authorities. For this level, only the “voluntary isolation of sick people” is to be applied, while further measures such as face masks, school closings, distance rules, contact tracing, vaccinations and lockdowns of entire societies are not recommended.

The new immunological results also mean that “immunity passports” and mass vaccinations are unlikely to work and are therefore not a useful strategy.

Some media continue to speak of allegedly much higher Covid lethality levels. However, these media refer to outdated simulation models, confuse mortality and lethality, or CFR and IFR, or “raw IFR” and population-based IFR. More about these errors here.

In July, an antibody prevalence of allegedly up to 70% was reported in some New York City districts. However, this is not a population-based figure, but rather antibodies in people who had visited an urgent care center.

The following graph shows the actual development of corona deaths in Sweden (no lockdown, no face mask obligation) compared to the forecasts of Imperial College London (orange: no measures; grey: moderate measures). Swedish annual all-cause mortality actually is in the range of a medium flu wave and 3.6% lower than in previous years.

Corona deaths in Sweden: ICL prediction versus reality (HTY/FOHM)

On the health risks of Covid-19

Why is the new coronavirus harmless for many people, but very dangerous for some people? The reason has to to with special features of the virus and the human immune system.

Many people, including almost all children, can neutralise the new corona virus with an existing immunity (due to contact with previous corona cold viruses) or through antibodies on the mucous membranes (IgA), without it causing much damage.

However, if this does not succeed, the virus can penetrate the organism. There the virus can cause complications in the lung (pneumonia), the blood vessels (thromboses, embolisms), and other organs due to its efficient use of the human ACE2 cell receptor.

If in this case the immune system reacts too weakly (in older people) or too strongly (in some younger people), the course of the disease can become critical.

It has also been confirmed that the symptoms or complications of serious Covid-19 disease can last for weeks or even months in some cases.

Therefore, the new coronavirus should not be underestimated and early and effective treatment is absolutely crucial for patients at risk.

In the longer term, the new coronavirus could develop into a typical cold virus, similar to the coronavirus NL63, which also uses the ACE2 cell receptor and nowadays affects primarily young children and nursing patients, causing upper and lower respiratory tract infections.

On the treatment of Covid-19

Note: Patients are asked to consult a doctor.

Several studies have now confirmed what some front-line physicians have been saying since March: Early treatment of Covid patients with zinc and the malaria drug hydroxychloroquine (HCQ) is indeed effective. US doctors have reported a reduction in hospitalisation rates of up to 84% and a stabilisation of the health condition often within a few hours.

Zinc has antiviral properties, HCQ supports zinc absorption and has additional antiviral properties. These drugs are supplemented by doctors if necessary with an antibiotic (to prevent a bacterial superinfection) and a blood thinner (to prevent infection-related thromboses and embolisms).

The alleged or actual negative results with HCQ in some studies were based, according to the current state of knowledge, on delayed use (intensive care patients), excessive doses (up to 2400mg per day), manipulated data sets, or ignored contraindications (e.g., favism or heart problems).

Sadly, the WHO, many media and some authorities may have caused considerable and unnecessary damage to public health in recent months through their negative stance, which may have been politically motivated or influenced by pharmaceutical interests.

French professor of medicine Jaouad Zemmouri, for example, estimates that Europe could have avoided up to 78% of Covid deaths by adopting a consistent HCQ treatment strategy.

HCQ contraindications such as favism or heart problems need to be considered, but the recent Ford Medical Center study achieved a reduction in hospital deaths of around 50% even with 56% African-American patients (who more often have favism).

However, the crucial point in the treatment of high-risk patients is early intervention as soon as the first typical symptoms develop and even without a PCR test in order to prevent progression of the disease and avoid intensive care hospitalization.

Most countries did the exact opposite: after the infection wave in March, they imposed a lockdown, so that infected and frightened people were locked up in their homes without treatment and often waited until they developed severe respiratory distress and had to be taken directly to the intensive care unit, where they were often sedated and intubated and were likely to die.

It is conceivable that a zinc HCQ combination protocol, which is simple, safe and inexpensive, could make more complex drugs, vaccinations and measures largely obsolete.

More recently, a case study from France showed that in four of the first five patients treated with the much more expensive drug Remdesivir from the pharmaceutical company Gilead, treatment had to be discontinued due to liver issues and kidney failure.

Read more: On the treatment of Covid-19

On the effectiveness of masks

Various countries have introduced or are currently discussing the introduction of mandatory masks in public transport, in shopping malls, or generally in public.

Some may argue that the discussion has become largely obsolete because of the lower-than-expected lethality and hospitalization rate of Covid-19 and the available treatment options, which have mostly eased the initial concern of “flattening the curve”.

Nevertheless, the question of the effectiveness of masks can be asked. In the case of influenza epidemics, the answer is already clear from a scientific point of view: masks in everyday life have no or very little effect. If used improperly, they can even increase the risk of infection.

Ironically, the best and most recent example of this is the often-mentioned Japan: Despite its ubiquitous masks, Japan experienced its most recent strong flu wave – with around five million people falling ill – just one year ago, in January and February 2019.

However, unlike SARS corona viruses, influenza viruses are transmitted also by children. Indeed, Japan had to close around ten thousand schools in 2019 due to acute outbreaks of the flu.

With the SARS 1 virus of 2002 and 2003, there is some evidence that medical masks can provide partial protection against infection. But SARS-1 spread almost exclusively in hospitals, i.e. in a professional environment, and hardly to the general public at large.

In contrast, a study from 2015 showed that the cloth masks in use today are permeable to 97% of viral particles due to their pore size and can further increase the risk of infection by storing moisture.

Some studies recently argued that everyday masks are nevertheless effective in the case of the new coronavirus and could at least prevent the infection of other people. However, these studies suffer from poor methodology and sometimes show the opposite of what they claim.

Typically, these studies ignore the effect of other simultaneous measures, the natural development of infection numbers, changes in test activity, or they compare countries with very different conditions.

An overview:

1. A German study claimed that the introduction of compulsory masks in German cities had led to a decrease in infections. But the data does not support this: in some cities there was no change, in others a decrease, in others an increase in infections (see graph below). The city of Jena, presented as a model, simultaneously introduced the strictest quarantine rules in Germany, but the study did not mention this.

2. A study in the journal PNAS claimed that masks had led to a decrease in infections in three hotspots (including New York City). This did not take into account the natural decrease in infections and other measures. The study was so flawed that over 40 scientists recommended that the study be withdrawn.

3. A US study claimed that compulsory masks had led to a decrease in infections in 15 states. The study did not take into account that the incidence of infection was already declining in most states at that time. A comparison with other states was not made.

4. A Canadian study claimed that countries with compulsory masks had fewer deaths than countries without compulsory masks. But the study compared African, Latin American, Asian and Eastern European countries with very different infection rates and population structures.

5. A meta-study in the journal Lancet claimed that masks “could” lead to a reduction in the risk of infection, but the studies considered mainly hospitals (Sars-1) and the strength of the evidence was reported as “low”.

The medical benefit of compulsory masks therefore continues to remain questionable. A comparative study by the University of East Anglia, for instance, came to the conclusion that compulsory masks had no measurable effect on the incidence of Covid infections or deaths.

It is also clear that widespread use of face masks couldn’t stop the initial outbreak in Wuhan.

Sweden showed that even without a lockdown, without mandatory masks and with one of the lowest intensive care bed capacities in Europe, hospitals need not be overburdened. In fact, Sweden’s annual all-cause mortality has remained in the range of previous flu seasons.

At any rate, authorities shouldn’t suggest to the population that mandatory masks reduce the risk of infection, for example in public transport, as there is no evidence of this. Whether with or without masks, there is an increased risk of infection in densely packed indoor areas.

Interestingly, the demand for a worldwide obligation to wear masks is led by a lobby group called “masks4all” (masks for all), which was founded by a “young leader” of the Davos forum.

Mandatory masks in German cities: no relevant impact. (IZA 2020)

The role of contact tracing

Numerous countries have introduced smartphone apps and special units for “contact tracing”. However, there is no evidence that these can make an epidemiologically relevant contribution.

In the case of tracing pioneer Iceland, the app has largely failed, in Norway it was stopped for data protection reasons, in India, Argentina, Singapore and other countries it became mandatory after all, in Israel contact tracing is operated directly by the secret service.

A WHO study on influenza pandemics in 2019 came to the conclusion that contact tracing is not useful from an epidemiological point of view and “is not recommended in any circumstances”. The typical area of application is rather sexually transmitted diseases or food poisoning.

Moreover, serious concerns about data protection and civil rights remain.

NSA whistleblower Edward Snowden warned as early as March that governments could use the corona crisis as an occasion or pretext for expanding global surveillance and control, thus creating an “architecture of oppression”.

A whistleblower who had taken part in a training program for contact tracers in the US described it as “totalitarian” and a “danger to society”.

Swiss computer science professor Serge Vaudenay showed that the contact tracing protocols are by no means “decentralized” and “transparent”, because the actual functionality is implemented through a Google and Apple interface (GAEN) that is not “open source”.

This interface has now been integrated by Google and Apple into three billion mobile phones. According to Prof. Vaudenay, the interface may record and store all contacts, not just those that are medically “relevant”. A German IT expert, for his part, described tracing apps as a “Trojan horse”.

For more information on “contact tracing”, see the June update.

See also: Inside the NSA’s Secret Tool for Mapping Your Social Network (Wired)

“Contact Tracing” powered by Google und Apple

On the origin of the new coronavirus

In the June update it was shown that renowned virologists consider a laboratory origin of the new coronavirus to be “at least as plausible” as a natural origin. This is due to some genetic peculiarities of the virus in the receptor binding domain, which lead to high infectivity in humans.

In the meantime, further evidence for this hypothesis has emerged. More in these articles:

· Covid-19 Virus Origin: The Mojiang Miners Passage Hypothesis (SPR)

· Seven year coronavirus trail from bat cave via Wuhan lab (London Times)

· Pentagon biolab discovered MERS and SARS-like coronaviruses in bats (DG)

Developments since the beginning of 2020 show that the new coronavirus cannot be seen as a “bioweapon” in the strict sense of the term, as it is not deadly enough and not targeted enough. However, it may well cause fear among the population and be exploited politically.

Nevertheless, besides a potential lab origin, a natural origin continues to be a realistic possibility, even though the “Wuhan wet market” hypothesis and more recently the pangolin hypothesis have in the meantime been ruled out by experts.

The Wuhan Institute of Virology (WIV)

Lisbon Court Rules Only 0.9% Of ‘Verified Cases’ Died Of COVID, Numbering 152, Not 17,000 As Claimed

via Great Game India
As per a ruling by the Lisbon court, only 0.9% of ‘verified cases’ died of COVID, numbering 152, and not 17,000 as claimed by the government. The ruling has proved that the government faked COVID-19 death statistics.

Following a citizen’s petition, a Lisbon court was forced to provide verified COVID-19 mortality data.

According to the ruling (read full judgment below), the number of verified COVID-19 deaths from January 2020 to April 2021 is only 152, not about 17,000 as claimed by government ministries.

All the “others” died for various reasons, although their PCR test was positive.

The data are from the Sistema de Informação dos Certificados de Óbito (Death Certificate Information System – SICO), the only such system in Portugal.

The reference to 152 death certificated issued ‘under Justice Ministry supervision’ is spurious, as all death certificates are issued under Justice Ministry auspices, being the only institution that issues them.

Last year, a Portuguese appeals court has ruled that PCR tests are unreliableand that it is unlawful to quarantine people based solely on a PCR test.

The court stated, the test’s reliability depends on the number of cycles used and the viral load present. Citing Jaafar et al. 2020, the court concludes that

“if someone is tested by PCR as positive when a threshold of 35 cycles or higher is used (as is the rule in most laboratories in Europe and the US), the probability that said person is infected is less than 3%, and the probability that said result is a false positive is 97%.”

In Germany, it was revealed according to extensive email exchanges obtained by a group of lawyers in a legal dispute, that the German Interior Ministry hired scientists to develop fake coronavirus model in order to justify strict lockdown.

England: 62% of “COVID” Deaths Are the Vaccinated

via: The Daily Expose

Breaking news on the morning of Friday June 25th revealed Matt Hancock has been having a secret affair with his aide Gina Coladangelo. We imagine it’s all the nation has been talking about since the images of Hancock embracing the millionaire lobbyist were published, it’s certainly all over the mainstream media and we doubt it will cease to be front page news any time soon.

But because you’ve been busy delighting in Hancock’s embarrassment, you’re probably not aware that Public Health England released a report on the very same day which showed the majority of alleged Covid-19 deaths are significantly higher in people who have had at least one dose of the Covid-19 vaccine, with the highest number of deaths occurring in people who are supposed to be fully vaccinated.

The report titled ‘SARS-CoV-2 variants of concern and variants under investigation in England’, is the 17th technical briefing on alleged variants of concern in the United Kingdom and makes for extremely interesting reading once you realise what the statistics are actually telling us.

PHE have compiled a helpful table which shows the number of alleged confirmed Delta variant cases in the UK alongside the number of alleged deaths due to the variant. The table shows that since the 1st February 2021 up to the 21st June 2021 there have been 9,571 alleged confirmed cases of the Delta variant in people over the age of 50. Of these 8,025 had been confirmed in the past 28 days alone.

But the data shows that people over the age of 50 who are unvaccinated account for just 10% of the alleged confirm Covid cases, whilst those who are fully vaccinated account for 37% of the alleged confirmed cases. A further 40% of the alleged cases are people who had received one dose of a Covid-19 vaccine at least 21 days prior to their alleged confirmed Covid-19 infection.

As you can see from the above table the number of people over 50 who are fully vaccinated with an alleged confirmed case of the Delta variant outnumber those who are unvaccinated by 3 to 1, whilst the number of people over 50 who have had at least one dose of the Covid jab and have an alleged confirmed case of the Delta variant outnumber those who are unvaccinated by nearly 9 to 1.

When the Covid-19 vaccines were given emergency use authorisation the authorities did not have a clue as to whether they would work. The limited trials carried out only measured whether or not a vaccinated person suffered serious disease if infected with Covid-19, they did not measure whether a vaccinated person could still become infected with Covid-19, and they did not measure whether or not a vaccinated person could still spread the virus in line with the mainstream accepted germ theory.

It is claimed that the vaccines reduce the chances of suffering serious illness if infected with Covid-19 significantly, so although a significantly higher amount of vaccinated over 50’s have a confirmed case of the Delta variant compared to those who are unvaccinated, you would assume that the opposite would be seen in the number of people who have allegedly died to the Delta variant?

Because Mr Hancock has told us time and time again that the Covid-19 vaccines are our only route back to normal and we must come forward, roll up our sleeves and get the jab when called upon to do so. So the vaccines must surely do what they say on the tin? It’s not as if Mr Hancock would lie to us, is it? He might have lied to his wife of fifteen years and engaged in an affair with an aide who he appointed to scrutinise the Department of Health as well as awarding her Taxpayers money for doing so, but he wouldn’t lie to the British people, would he?

Unfortunately, it looks like Mr Hancock has been lying again and instead of the Covid-19 vaccines being our route back to normal they are instead quite the opposite. Because the data published by Public Health England shows us that the number of alleged deaths due to the Delta variant are highest among those who have received two doses of the vaccine. [That’s only true in the absolute. ]

Of the 117 alleged Covid deaths to have occurred since the 1st February, a huge 60% of them were people who had received at least one dose of a Covid-19 vaccine which is allegedly supposed to protect them from serious illness. But the majority were not people who had only received one dose, 70% of those who had died even after at least one dose of the Covid-19 jab were in fact fully vaccinated, and a further 27% of those who’d had at least one dose had received their first dose at least 21 days prior to their death.

The number of unvaccinated people to have allegedly died of the Delta variant accounted for just 37% of all alleged Covid deaths according to PHE data.

PHE also revealed just how frighteningly dangerous the Delta variant is within their report. Table 2 shows us that the case fatality rate for the Delta variant is an astronomical 0.1%.

We wonder if you were surprised as we were to see a fatality rate as low as 0.1%? Maybe it’s a mistake, because the people who religiously watch BBC news, trust the Government, and the WHO, wear a mask religiously, preach to others that there’s nothing to worry about when it comes to taking an experimental vaccine because “science is just quicker now”, and attempt to coerce others into getting the jab because “the delta variant is really dangerous”, can’t all be wrong, can they?

2009, Project Depopulation: Bill Gates Gathers the World’s Top Billionaires

by tts-admin via The Truth Seeker

Dean W. Arnold – Dean W. Arnold.com April 29, 2021

  • Excerpted from Dean Arnold’s book exposing Gates and his population control efforts in Ethiopia and Africa.

On May 5, 2009, Bill Gates gathered together a handful of the West’s richest men who met in Manhattan to discuss what they considered the most dangerous, most critical threat to the planet.

Those attending included Warren Buffett, Ted Turner, George Soros, and David Rockefeller, Jr. What did they deem the world’s biggest threat? They each gave a 15-minute presentation on their primary concern for the planet. “Taking their cue from Gates, they agreed overpopulation was a priority,” according to the report from London’s Sunday Times.

Meanwhile, the staffers of the oligarchs were told that “security briefings” were the reason for their meeting. “We only learned about it afterward,” said Stacy Palmer, editor of the Chronicle of Philanthropy. “Normally these people are happy to talk about good causes, but this is different—maybe because they don’t want to be seen as a global cabal.” [1]

Gates meeting was a great success, as his billionaire friends and all the major foundations decided to contribute to the Gates Foundation’s population control efforts. Warren Buffett, the second richest at the time behind Gates, shifted $31 billion of his assets to his friend Bill. In 2011, Gates told CNN: “The benefits [of vaccines] are there in terms of reducing sickness, reducing population growth.” In a 2010 Ted Talk he said, “If we do a really great job on new vaccines, health care, reproductive health services, we could lower [population] by perhaps ten or fifteen percent.”

Such quotes alarmed many that Gates’ obsession with vaccines might be accompanied by a sinister agenda for population reduction. This concern materialized in Kenya in 2014 when of 3 million women there unknowingly received vaccinations from the Gates-funded World Health Organization that were secretly laced with a sterilant and contraceptive. The WHO denied it, but in 2017, the former prime minister of Kenya, Raila Odinga backed the doctors: “Today, we can confirm to the country that the Catholic Church was right.” [2]

My. My second article this week documents that Gates, along with George Soros, is a key donor for the Lucis Trust, originally named after Lucifer.

What about the others attending that 2009 meeting, such as David Rockefeller? The Rockefeller Foundation funded Margaret Sanger in her early years. A little research on the Kenya HCG vaccine that sterilizes women also brings to the fore the Rockefeller family. I tracked down the Rockefeller Foundation’s 1968 Annual Report. On page 52, it calls for “progress on immunological methods, such as vaccines, to reduce fertility.” Their 1988 Annual Report cites a large grant given to India for “a large anti-fertility vaccine for women.” Another generous grant is listed on page 56 “for research on a potential contraceptive vaccine based on beta-hCG synthesized bacteria”—just a few years before the 1993 experiments in Mexico, Nicaragua, and the Philippines. [3]

Let’s look at one more member of the famous 2009 meeting of oligarchs in Manhattan—Ted Turner. The founder of CNN has been concerned about overpopulation for decades. In 1996, he told Audubon magazine, “We’re all 5 billion of us on this little earth swimming around in space, and there’s too many of us,” he said. “If we had a much smaller population . . . we could cut back to 250 million—350 million people.”

Turner’s longings are memorialized by a monument of huge, druid-like stone tablets that sit atop a rural hill in Elbert County, Georgia, 30 minutes from CNN headquarters. Yoko Ono wrote a musical score with John Cage in three movements to honor these “Georgia Stones,” which proclaim in eight languages the “Ten Guides” for the billions of people now on earth.

The First Guide says in engraved script: “Maintain humanity under 500 million in perpetual balance with nature.” [4]

There are no instructions for how to get from today’s 7+ billion down to 500 million people, causing us to wonder what kinds of plans were being made by Turner, Gates, Rockefeller and the others at their secret meeting in 2009.

The inscriptions on the mysterious Georgia Guidestones also allude to a massive reduction in the world population.

UNEP, the United Nations Environment Program, quoted an expert in its Global Biodiversity Assessment Report: “A reasonable estimate for an industrialized world society at the present North American material standard of living would be 1 billion. At the more frugal European standard of living, 2 to 3 billion would be possible.”

Some high-profile figures, however, have called for a deliberate attempt by world leaders to kill off large segments of the population. In a 1991 United Nations publication, world famous oceanographer Jacques Cousteau said: “It’s terrible to have to say this: World population must be stabilized, and to do that we must eliminate 350,000 people per day. Prince Philip, royal spouse of Queen Elizabeth, declared his ambition to solve the “population explosion” by being reincarnated as a “particularly deadly virus.” Bertrand Russell, the famous atheist philosopher and humanist leader, celebrated worldwide by population control institutions, provided a careful, reasoned quote to help understand how rational people just might consider eliminating half of humanity.

“I do not pretend that birth control is the only way in which population can be kept from increasing,” wrote Russell in The Impact of Science on Society. “War so far has had no great effect on this increase . . . perhaps bacteriological war may prove more effective. If a Black Death could be spread throughout the world once in every generation, survivors could procreate freely without making the world too full . . . the state of affairs might be somewhat unpleasant, but what of it? Really high-minded people are indifferent to suffering, especially that of other people’s.” [5]

Bertrand Russell received the Nobel Prize for literature. He was by all accounts a cordial man. And he dressed nicely.

Again, it is difficult for all of us to imagine “nice” people thinking this way, or acting upon it. However, the elite mentality has always been with us, since Plato wrote his Republic 2300 years ago. Every kid studies this book at prep schools like the Gates’s attended. This most famous of Greek philosophers told us that the ruling class are those “whose aim will be to preserve the average of population.” He further stated, “There are many other things which they will have to consider, such as the effects of wars and diseases and any similar agencies, in order as far as this is possible to prevent the State from becoming either too large or too small.”

Plato adds that population control must be done in secret—what you might call a conspiracy. “Now these goings on must be a secret which the rulers only know, or there will be a further danger of our herd… breaking out into rebellion.”

David Rockefeller. Truly he wouldn’t be out of place in a Dracula or Frankenstein movie.

In his 2003 memoirs, David Rockefeller does nothing to dispel the notion that Plato’s Republic is the oligarch’s go-to playbook: “Some even believe we are part of a secret cabal working against the best interests of the United States, characterizing my family and me as ‘internationalists’ and of conspiring with others around the world to build a more integrated global political and economic structure — one world, if you will. If that is the charge, I stand guilty, and I am proud of it.” [6]

The Rockefellers have another black mark on their record that is particularly egregious. Dr. Gregory Pincus, who helped Sanger develop the birth control pill, studied and worked with the Rockefeller funded Kaiser Wilhelm Institute, exposed for sterilizing 600 French African children and closely associating with the Nazi eugenics program. The Kaiser Wilhelm Institute was in fact the primary driver of eugenics in Hitler’s Third Reich, overseeing a complex of hospitals and research centers, including the Kaiser Wilhelm Institute of Anthropology, Human Heredity and Eugenics. Hitler was highly influenced by the first director, Eugen Fischer, and his two volume Principles of Human Heredity and Race Hygiene. Many ideas from this book reappear in Hitler’s Mein Kampf. Dr. Karin Magnussen conducted experiments at the Kaiser Wilhelm Institute on eye color to prove Nazi racial theories, and her eye specimens were supplied from concentration camps by famous Nazi Dr. Joseph Mengele. When funding began to fall, the Kaiser Wilhelm Institute’s eugenicist center looked to the Rockefellers, who provided more support. [7]

ENDNOTES

[1] “Billionaire club in bid to curb overpopulation” The Times, May 24, 2009, https://www.thetimes.co.uk/article/billionaire-club-in-bid-to-curb-overpopulation-d2fl22qhl02(Retrieved April 22, 2019).

[2] “reducing population growth”Bill Gates 2011 interview with CNN’s Dr. Sanjay Gupta, (28 second mark), https://youtu.be/U_Gi6cf-jiI see also, https://jasperandsardine.wordpress.com/2015/06/05/pro-vaccine-fanatic-bill-gates-funds-predictive-model-showing-33-million-people-dead-from-spanish-flu-pandemic.

“lower [population] by perhaps 10 or 15 percent”2010 Ted Talk transcript, https://www.ted.com/talks/bill_gates/transcript?language=en ;
2010 Ted Talk video, “Innovating to Zero!” https://www.ted.com/talks/bill_gates?language=en(Retrieved April 22, 2019).

“Catholic Church was right” “Kenya—Thousands infertile after gov’t sponsored vaccination—Odinga,” Agence de Presse Africaine, Sept. 11, 2017, http://apanews.net/en/pays/kenya/news/kenya-thousands-infertile-after-govt-sponsored-vaccination-odinga (Retrieved April 25, 2019).

[3] “[Sanger’s first] clinic received extensive funding from John D. Rockefeller, Jr. and his family, who continued to make anonymous donations to Sanger’s causes in subsequent decades.” Wikipedia: Margaret Sanger, sourcing Ellen Chesler, Woman of Valor: Margaret Sanger and the Birth Control Movement in America (New York: Simon and Schuster, 2007), p. 277, 293, 558.

“President’s Five-Year Review & Annual Report,” The Rockefeller Foundation, 1968, p. 52, 22, 56 https://assets.rockefellerfoundation.org/app/uploads/20150530122242/Annual-Report-1968.pdf(Retrieved April 25, 2019). [Note: this link has disappeared since my book was written, but I saved the document and it is uploaded here: http://deanslist.info/wp-content/uploads/2020/04/Annual-Report-1968.pdf ]

1988 Rockefeller Foundation Annual Report: http://deanslist.info/rockefeller-foundation-annual-report-1988/annual-report-1988/

[4] Bruce Stutz, “Ted Turner Turns it On,” Audubon, November-December, 1991. Vol. 93, No. 6), p. 113. See screenshot at https://notunlikelee.wordpress.com/tag/audubon-magazine/ (Retrieved April 25, 2019).

Randall Sullivan, “American Stonehenge: Monumental Instructions for the Post-Apocalypse,” WIRED, April 20, 2009, https://www.wired.com/2009/04/ff-guidestones/?currentPage=1(Retrieved April 26, 2019).

[5] Global Biodiversity Assessment of UNEP (United Nations Environment Program), Section 9, phase One Draft, Section 9.2.3.2, p. 108 (See also Global Biodiversity Assessment. Cambridge: Cambridge University Press) 1995, p. 773), cited in Henry Lamb, “The Rise of Global Governance,” Institute for Agriculture & Trade Policyhttps://www.iatp.org/sites/default/files/Global_Governance_Why_How_When.htm#91 (Retrieved April 26, 2019).

“Interview: Jacques-Yves Cousteau,” The UNESCO Courier, Nov. 1991, p. 13 https://joseywales1965.files.wordpress.com/2014/06/0003_jacques_couteau.pdf (Retrieved April 25, 2019).

“Foreword by Prince Philip,” Fleur Cowles, If I Were an Animal (New York: Morrow, 1987), cited in Wikiquote: Prince Philip, Duke of Edinburgh https://en.m.wikiquote.org/wiki/Prince_Philip,_Duke_of_Edinburgh (Retrieved April 26, 2019).

Bertrand Russell, The Impact of Science Upon Society (New York: AMS Press, 1968), p. 103-104https://ia600300.us.archive.org/0/items/TheImpactOfScienceOnSociety-B.Russell/TheImpactOfScienceOnSociety-B.Russell.pdf (Retrieved April 26, 2019).

[6] Plato, The Republic, Book V, in The Dialogues of Plato , Vol II (New York: Charles Scribner and Company, 1871), p. 285.

David Rockefeller, Memoirs (New York: Random House, 2003), p. 406.

[7] “studied and worked with Kaiser” “Dr. Pincus, Developer of the Birth Control Pill, Dies,” New York Times, Aug. 23, 1967 https://archive.nytimes.com/www.nytimes.com/learning/general/onthisday/bday/0409.html(Retrieved April 26, 2019).

“sterilizing 600 French African children” Helga Kuhse and Peter Singer, Bioethics: an anthology(Wiley-Blackwell, 2006), p. 232, cited in Wikipedia: Kaiser Wilhelm Institute of Anthropology, Human Heredity, and Eugenics https://en.wikipedia.org/wiki/Kaiser_Wilhelm_Institute_of_Anthropology,_Human_Heredity,_and_Eugenics (Retrieved April 26, 2019).

“Hitler highly influenced by” A. E. Samaan, From a Race of Masters to a Master Race: 1948 To 1848 (A.E. Samaan/CreateSpace, 2014) p. 539 https://books.google.com/books?id=JkXJZtI9DQoC&printsec=frontcover#v=onepage&q&f=false (Retrieved April 26, 2019).

“Eye experiments” Hans-Walter Schmuhl, The Kaiser Wilhelm Institute for Anthropology, Human Heredity and Eugenics, 1927-1945. Wallstein Verlag: Gottingen, 2003), p. 410, cited in “Eugenics – Karin Magnussen,” Esther M. Zimmer Lederberg Memorial Websitehttp://www.estherlederberg.com/Eugenics%20%28CSHL_List%29/Karin%20Magnussen.html(Retrieved April 26, 2019).

“Financial help” Edwin Black, “Eugenics and the Nazis—the California connection,” San Francisco Chronicle, Nov. 9, 2003 https://www.sfgate.com/opinion/article/Eugenics-and-the-Nazis-the-California-2549771.php (Retrieve d April 26, 2019).

Dr. Peter McCullough: ‘whistleblowers’ inside CDC claim injections have already killed 50,000 Americans

‘Good doctors are doing unthinkable things’ …They ‘appear to be under a spell’

via LeoHohmann.com

Dr. Peter McCullough

The most highly cited physician on the early treatment of COVID-19 has come out with an explosive new video that blows the lid off the medical establishment’s complicity in the unnecessary deaths of tens of thousands of Americans.

Dr. Peter McCullough said these deaths have been facilitated by a false narrative bent on pushing an all-new, unproven vaccine for a disease that was highly treatable.

He said COVID was a bioweapon and the vaccines represent “phase two” of that bioweapon.

“As this, in a sense, bioterrorism phase one was rolled out, it was really all about keeping the population in fear and in isolation and preparing them to accept the vaccine, which appears to be phase two of a bioterrorism operation,” McCullough said in a June 11 webinar with German attorney Reiner Fuellmich and several other doctors.

He noted:

“Both the respiratory virus and the vaccine delivered to the human body the spike protein, the gain of function target of this bioterrorism research.”

Most of McCullough’s comments come in the first 10 minutes of the below video.

“Now I can’t come out and say all this on national TV today or at any time,” he continued. “But, what we had learned over time is that we could no longer communicate with government agencies. We actually couldn’t even communicate with our propagandized colleagues in major medical centers, all of which appear to be under a spell, almost as if they are hypnotized right now.”

He did not hold back in his criticism of his colleagues in the medical community.

“And doctors, good doctors, are doing unthinkable things, like injecting biologically active messenger RNA that produces this pathological spike protein into pregnant women. I think when the doctors wake up from their trance they’re going to be shocked to think what they’ve done to people.”

McCullough is professor of medicine and vice chief of internal medicine at Baylor University and also teaches at Texas A&M University. He is an epidemiologist, cardiologist and internist and has testified before the Texas State Senate related to COVID-19 treatments. He holds the distinction of being the most widely cited physician in the treatment of COVID-19 with more than 600 citations in the National Library of Medicine.

In the video, recorded by Oval Media, McCullough said:

“The first wave of the bioterrorism is a respiratory virus that spread across the world, and affected relatively few people—about one percent of many populations—but generated great fear.”

He said the virus targeted primarily people over 50 with multiple medical conditions. It poses almost no risk to children.

He said 85 percent of the more than 600,000 U.S. deaths could have been prevented with a multi-drug treatment given in the early to mid-point of the disease.

Instead, people were told to stay home and not return to the hospital unless their symptoms got worse, such as severe breathing problems. By then it was too late for many. They were placed on ventilators and died.

The vast majority of doctors jumped in lockstep to follow these erroneous “guidelines” handed down by the World Health Organization and the U.S. Centers for Disease Control. Those guidelines neglected to place any focus on the treatment of sick patients and, from the beginning, as early as April 2020, started emphasizing the need for a vaccine as the only real hope of beating back the virus.

The federal Vaccine Adverse Event Reporting System [VAERS] logged 5,993 reports of deaths of people injected with the COVID vaccine between Dec. 14, 2020, and June 11, 2021. That’s more than all the deaths reported to VAERS from all other vaccines combined over the last 22 years.

But these numbers, as shocking as they are, don’t scratch the surface of the actual number of dead Americans, said McCullough.

“We have now a whistleblower inside the CMS, and we have two whistleblowers in the CDC. We think we have 50,000 dead Americans. Fifty thousand deaths. So we actually have more deaths due to the vaccine per day than certainly the viral illness by far. It’s basically propagandized bioterrorism by injection.”

McCullough added that “every single thing that was done in public health in response to the pandemic made it worse.”

He said the suppression of early COVID treatments, such as hydroxychloroquine and especially Ivermectin, “was tightly linked to the development of a vaccine.”

Without the suppression of the already-available treatments, the government would not have been able to legally grant Emergency Use Authorization to the three vaccines rushed to market by Moderna, Pfizer and Johnson and Johnson.

In the case of Moderna, the U.S. government is co-patent holder through the National Institutes of Health, a clear conflict of interest.

“I published basically the only two papers that teach doctors how to treat COVID-19 at home to prevent hospitalization and death…If treated early, it results in an 85 percent reduction in hospitalizations and death,” McCullough said.

So not only were the vaccines rolled out unnecessarily by suppressing already available, effective treatments, but the FDA and CDC are now covering up tragic numbers of deaths caused by their experimental mRNA injections.

McCullough said he has organized groups around the world that emphasize early treatment.

“Governments have actually tried to block early treatment of COVID patients, so we created a home patient guide,” he said.

“We broke through to the people, and the people who got sick with COVID called in to get medications from mail-order distribution pharmacies. So without the government even knowing what went on, we crushed the epidemic here in the United States towards the end of December and January. We basically took care of the pandemic with about 500 doctors and telemedicine services. And to this day we treat about 25 percent of the US COVID-19 population that actually are at high risk, over age 50 with medical problems or present with severe symptoms. And we basically handled the pandemic, and at the same time we’ve tried to keep ourselves above the political fray.”

McCullough said his focus has recently turned to the unnecessary and dangerous injections.

“We are working to change the public view of the vaccine. The public initially accepted the vaccine and we had to kind of slowly turn the ship. Now, in the U.S. the rates of vaccination have been dropping since April 8. Most of the vaccination centers are empty.”

“We have a lot going on in the United States. We are engaging more and more attorneys.”

London Protests Against the Lockdown

Massive crowds took to the streets of London today to protest against COVID tyranny.

Video footage from the air and on the ground show massive crowds.

The sign this woman is holding in the first frame of the video clip below:

We’re Not From the Left or Right We’re From the Bottom and We’re Coming for Those on TOP!

It appears that race and political affiliation were put aside in this protest, which is what is needed if the masses are going to have any effect against the Globalists.

Saving the children from the bioweapon shots seemed to be a common theme.

People dancing to the song by British Rock Band Pink Floyd “Brick in the Wall”

And where are similar protests in the USA?

Oh, that’s right. You have to go to a public school board meeting to see parents up in arms about COVID measures because they want to keep using the Nanny State’s school system to babysit their children so they don’t have to.

And if we do see protests, they will probably be much smaller than this one in London today, with BLMers on one side and Trump supporters on the other, and they won’t be protesting against the Globalists, but fighting each other instead.

If the masses do rise up together to overthrow tyranny, I’d bet on the UK over the US any day. It looks like they are fairly unified in taking down Boris Johnson and the rest of the hoodlums in Parliament.

Death By Vaccine – The Greatest Scandal Of 21st Century

via Great Game India

In his book Deadly Medicines and Organized Crime, Dr. Peter Gotzsche arguably recognized as one of the world’s foremost experts in evaluating evidence-based medicine (EBM) writes, “The reason why we take so many drugs is that drug companies do not sell drugs. They sell lies about drugs…. The patients do not realize that although their doctors know a lot about diseases, human physiology and psychology, they know very little about the drugs that have been concocted and dressed up by the drug industry.”

An issue that is rarely discussed or given serious attention is the over-specialization in healthcare. Modern medicine’s approach to identify and treat illnesses and tackle the reduction of infections has in many instances ceased to be multidisciplinary.

Medicine has also become increasingly compartmentalized and confined to a rigid materialistic belief system that has now established its own set of standards, criteria and values that are often contrary to gold-standard scientific protocols. The consequence is that its narrow single-mindedness has insulated modern medicine from objective criticism and preserved its internal flaws, errors and fabrications, which have contributed to the unnecessary injury and death of countless patients

US healthcare spending reached $3.8 trillion in 2019. Due to the Covid pandemic, expenditures for 2020 will be astronomically higher. One might expect that with the world’s most expensive healthcare system, the US would equally have the best evidence-based practices to keep its citizens healthy. By now we should be proficiently expert at preventing and reversing disease, while making minimal errors resulting in injury or death.

However, the exact opposite is the case. Instead of minimizing disease-causing factors, American medicine causes more illness through misguided diagnostic testing, overuse of medical and surgical procedures, and over prescribing pharmaceutical drugs. The fundamental reason for this catastrophe is that today’s healthcare establishment, and corporate science in general, over relies on profit-generating motives.

Dr. Peter Gotzsche is arguably recognized as one of the world’s foremost experts in evaluating evidence-based medicine (EBM). As the co-founder of EBM’s preeminent flagship organization – the Cochrane Collaboration — to review and analyze peer-reviewed clinical research, he is intimately knowledgeable about the widespread corruption permeating the pharmaceutical industry and medical journals. In his book Deadly Medicines and Organized Crime, he writes,

“The reason why we take so many drugs is that drug companies do not sell drugs. They sell lies about drugs…. The patients do not realize that although their doctors know a lot about diseases, human physiology and psychology, they know very little about the drugs that have been concocted and dressed up by the drug industry.”

After we take a fair and objective look at American medicine during the past five decades, especially at the statistics of iatrogenic fatalities, or deaths caused by prescribed medications and medical error, our healthcare establishment is found to be anything but benign.

Despite its many noteworthy discoveries and merits, a substantial amount of recommended medical practice has failed patients.

“If the medical system were a bank,” writes Dr. Stephen Persell at Northwestern University’s School of Medicine, “you wouldn’t deposit your money here, because there would be an error every one-in-two to one-in-three times you made a transaction.” Dr. Persell is referring to the rates of preventable medical errors causing patients serious injury and now the third leading cause of death.

There is excellent evidence to support the argument that iatrogenic deaths have passed cancer fatalities and are now challenging heart disease for the number one spot. A 2008 study found as many as half of adverse events reported by patients were not recorded in their hospital charts.

As of 2017, investigations continue to find that less than 10% of medical errors are reported. Reported adverse effects vary depending on the specialty and frequently go unnoticed or are improperly evaluated. An additional study found that almost two thirds of cardiologists had refused to report a serious error they had direct personal knowledge of to an authority.

As one example, heart disease is America’s leading cause of fatality, accounting for 665,000 deaths annually. The CDC, which consistently undermines health threats if it means positioning itself in opposition to private commercial interests, estimates that 34 percent of cardiovascular fatalities are premature and preventable.

In contrast, the American Heart Association claims 80 percent are preventable. What are the heads of our federal health agencies doing to advocate on the side of prevention? Little to nothing.

There is no realistic and science-based national policy in place to lessen cardiovascular, cancer and diabetic death rates. Since the most viable and effective means to prevent these diseases are natural and within every person’s means, it is not financially lucrative to divert federal funding away from pharmaceutical treatments and surgical procedures. The CDC and FDA are largely dependent upon monetary income received from the drug and medical device industries.

Earlier we reported about the systemic corruption and fraud that has plagued the CDC and FDA for decades. It would be far cheaper to completely empty, dismantle, fumigate and rebuild the agencies anew rather than continue exerting pressure for reforms, which have only perpetuated a killing spree by protecting life-threatening drugs, vaccines and unnecessary medical procedures.

Dr. Gotzsche notes, the same is true for private drug companies. Despite the numerous lawsuits drug companies have lost in federal courts, nothing has fundamentally changed in order to deter them from illegal activities to increase profits. In fact, the cost of paying out settlements and settling lawsuits is factored into the expense of doing business.

A decade ago, we teamed up with three board-certified physicians to undertake the task to review the peer-reviewed literature in order to recalculate the statistics from many branches of medicine in order to arrive at a more realistic casualty rate due to medical error.

We began with a basic question. Do the current standards of American medical practice and its supporting science prove that the recommended therapies and healthcare protocols – whether drugs, surgery, diagnostic methods, medical devices, etc – are actually effective? And if so, at what cost to the patients’ health and well-being?

Our results and final conclusions were startling and culminated in the release of a widely read and referenced book, Death by Medicine. We made every effort to avoid editorial commentary to our findings. We decided to only report the statistics and facts with our calculations. The fact that our data placed iatrogenic error as the number one cause of death in America was alone sufficient.

What was novel in our analysis was that we included preventable deaths, such as certain infections and severe nutrient deficiency, which could have been easily corrected by clinicians and medical personnel if viable prevention programs had been part of our healthcare system.

After publication the book was sent to hundreds of journalists, federal officials and non-profit medical organizations. It was completely ignored by the orthodoxy; however, it became increasingly popular among alternative and complementary medical physicians who were already fully aware of the structural dangers to public health within conventional medical care.

Revisiting American medicine’s legacy of iatrogenic deaths is now more crucial than ever because the same behaviors that have contributed to the nation’s leading cause of death are being repeated during the Covid-19 pandemic. The government and federal health officials are in reprehensible denial of inexpensive and highly effective drugs, such as Ivermectin and hydroxychloroquine, to treat early and middle stage SARS-2 infections.

Cases of Covid infections and deaths have been grossly exaggerated. And now we are realizing that the efficacy and safety profiles of the vaccines are orchestrated scams. As a result, the entire institutional edifice to vaccinate the global population is destined to become the greatest scandal of the 21st century.

Unfortunately, nobody can acquire accurate statistics for Covid-19 vaccine associated injuries and deaths from the CDC’s Vaccine Adverse Events Reporting System (VAERS). Careful weekly monitoring of VAERS’ adverse event updates convince us that the entire system is criminally rigged.

CDC officials overseeing the database are undoubtedly fudging numbers after ratio of adverse events, including deaths, per number of doses administered are compared to the more robust and accurate EudraVigilance database in the European Union and the less reliable Yellow Card System in the UK.

As of June 17, VAERS was reporting 329,021 injuries and 5,888 deaths due to the Covid vaccines. The database’s most recent update is reporting an additional 26,541 injuries but 1,972 less deaths. How can this sudden disappearance of almost 2,000 deaths be accounted for?

The mysterious loss of fatality entries occurred during the same week as a CDC working group of outside medical professionals was reviewing an association between the mRNA vaccines and the rising number of reported cases of cardiac inflammation or myocarditis.

The group concluded that there is indeed “a likely association.” The occasion of deleted deaths in VAERS is also on the heels of the Israeli Shamir Medical Center report that Pfizer’s vaccine is linked with occurrences of thrombotic thrombocytopenic purpura, an autoimmune disorder associated with a rare form of blood clotting.

However, despite weekly local news stories around the nation about youth as young as 19 years of age dying of vaccine complications shortly after receipt of an mRNA vaccine, the CDC is claiming that all 1,200 persons, between 16-24 years of age, recovered and no deaths were reported. Does this account for the likely scrubbing of entries in VAERS?

But it is much worse. We only need to look at the European Union’s statistics for adverse Covid-19 vaccine events and compare that with VAERS and the CDC’s recent conclusion to realize there is a massive cover-up in our government’s efforts to sanitize the safety record of Covid vaccines.

As of this week the EudraVigilance system is reporting over 1.5 million injuries and 15,472 deaths. Within those figures, 28,583 injuries and 1,862 deaths are from cardiac complications such as myocarditis.

Second, the EU and US have administered approximately the same number of Covid vaccine doses, roughly 409 million and 379 million respectively. Therefore we should expect to find a similar dose-to-injury ratio.

Again we discover the CDC gaming the nation’s reporting system to lessen the perception of lethal risks. Based upon the EU ratio we can conservatively estimate that a minimum of 14,300 Americans have been killed by the vaccines so far. If we go back a week before the CDC scrubbed entries in VAERS, it would be over 17,000 Covid vaccine deaths. The actual number of Americans suffering adverse reactions would be 1.4 million.

In other words the EU is reporting 4 times more vaccine injuries and deaths than American health officials. In both the US and EU, Pfizer’s mRNA vaccine accounts for the majority of these casualties. Unless the Covid-19 vaccines engineer a personal vendetta against people holding EU passports, these numbers don’t add up.

Before the arrival of the Covid vaccines, Merck’s anti-inflammatory drug Vioxx was widely regarded as the single largest pharmaceutical catastrophe in American medical history. The drug should never have been approved and licensed in the first place; and, Merck knew beforehand that the drug would be lethal and concealed that documentation from FDA regulators.

Vioxx was on the market for five years before being withdrawn. At the time of the federal class action lawsuit against Merck, FDA epidemiologist Dr. David Graham estimated the drug had killed 60,000 patients due to heart attacks and strokes.

Since the majority of deaths were among elderly patients, a later report by the American Conservative predicted that upwards to half a million patients may have died from the drug over the course of a longer period. Yet during those years Merck was cashing in $2 billion annually from Vioxx sales, earning over double its eventual $4.8 billion fine after being found guilty.

To put this into a broader perspective, the Covid vaccines have only been distributed for six months and have now contributed to a realistic 17,000 deaths or upwards towards 30,000 this year alone. Since the vaccines’ immunity quickly wanes and it seems certain they provide little protection against new SARS-2 strains, health officials are already recommending regular booster shots.

Similar to a prescription medication, those who buy into the vaccine propaganda hype are in principle relying upon these vaccines for life or until such time the virus subsides into just a seasonal nuisance. Consequently iatrogenic vaccine injuries and deaths may likely continue at current rates during forthcoming years.

The Covid-19 vaccines are on track to outpace the conservative number of Vioxx deaths over three-fold and even modern medicine’s most deadly drug Cerivastatin, manufactured by Bayer in the late 1990s and responsible for over 100,000 deaths during the four-year period it was on the market. In short time, Covid vaccines will be the deadliest drug to have emerged from Big Pharma.

A study published in the Journal of Patient Safety estimated that 400,000 unnecessary and preventable deaths occur annually in American hospitals alone. At that rate, it is not surprising that the large majority of deaths ruled as SARS-2 infections happened in hospitals.

If our federal health officials had been competent, and less compromised by the demands and influence of drug makers, most of these fatalities likely would never have occurred.

It has been estimated that US taxpayers have paid out $39 billion for Covid-19 vaccine development, funding and towards nationalized response measures. Most of this has been horribly wasted after we consider other options on hand to curb the pandemic but were categorically ignored. “In the case of vaccines in general,” the journal Health Affairs observed,

“the government often plays an outsized role, but in the era of Covid-19 the government’s role was even more central than usual. The government essentially removed the bulk of traditional industry risks related to vaccine development: a) scientific failures, b) failures to demonstrate safety and efficacy, c) manufacturing risks, and d) Market risks related to low demand.”

While this may shock and disturb a rational person, Health Affairs – a thoroughly orthodox medical publication – applauds the government’s negligent measures as “money well spent.”

For this reason it is crucial to understand the terrible decisions made during the Covid pandemic in the context of modern medicine’s past crimes and preventable failures.

In the coming months Anthony Fauci’s reputation will become further tainted. We might predict he will resign as more evidence of incompetence emerges, and, in our opinion, perhaps criminal negligence in his handling of the pandemic and efforts to whitewash the US’s role in supporting gain of function research leading to the genetic engineering of the SARS-2 virus.

Fortunately, unlike past scandals when misguided medical decisions were responsible for thousands of unnecessary disabilities and deaths, numerous doctors and scientists worldwide are raising their voices to condemn the lethal policies of the CDC, NIAID, British Health Ministry and the World Health Organization.

So what can we reasonably surmise at this point? At one time most Americans trusted science, medicine and our healthcare system without question or criticism. However, today we observe systemic corruption and gross conflicts of interest across same federal health agencies that have also contributed to untold medical errors and deaths prior to SARS-2 arrival.

They have weaponized pharmaceutical science and a supplicant braying media supports this perversion of medical facts. Now the drug-happy media is attacking the truth-tellers, the physicians, professors and accomplished journalists who are risking their careers and reputations to bring forth the fallacies in the pandemic narrative. This is one battle that the silent majority can find its voice and courage to step forth and support.

Richard Gale and Gary Null PhD, Progressive Radio Network, June 25, 2021

Richard Gale is the Executive Producer of the Progressive Radio Network and a former Senior Research Analyst in the biotechnology and genomic industries.

Dr. Gary Null is the host of the nation’s longest running public radio program on alternative and nutritional health and a multi-award-winning documentary film director, including Poverty Inc and Deadly Deception.

2017 Johns Hopkins Document Called “SPARS 2025-2028” Mirrors Today’s COVID Crisis

via: Centipede Nation

A 2017 document by Johns Hopkins is currently going viral which details plans for a global medical response under a hypothetical ‘exercise’ pandemic named “SPARS 2025-2028”, mirroring today’s world scenarios under COVID-19.

From John Hopkins’ centerforhealthsecurity.org:

The Center’s SPARS Pandemic exercise narrative comprises a futuristic scenario that illustrates communication dilemmas concerning medical countermeasures (MCMs) that could plausibly emerge in the not-so-distant future.

[…]The self-guided exercise scenario for public health communicators and risk communication researchers covers a raft of themes and associated dilemmas in risk communications, rumor control, interagency message coordination and consistency, issue management, proactive and reactive media relations, cultural competency, and ethical concerns.

The most interesting thing about this document is how it mirrors and outlines the entirety of the current Plandemic. The similarities are uncanny, including strategies for the MSM, presidents and celebrities being used to sell the vaccines – to the actual fatality rates being ‘predicted’ along with the numbers, to tweets and marketing campaigns, to “isolation procedures”. They even planned in advance how to counter people’s arguments on social media that question the side effects of the experimental vaccines, including calling everyone questioning the main narrative a conspiracy theorist.

Some people on social media have commented that the paper was basically a retrospective on the past year, and asked the questions about where the breakdowns in communication were. The interesting part is that while it reads like a retrospective of the past year, the John Hopkins website says that it was completed in October 2017.

Highlights

  • “After showing no adverse side effects for nearly a year, vaccine recipients slowly began to experience symptoms.”
  • “As time passed and more people across the United States were vaccinated, claims of adverse side effects began to emerge.”
  • “As the investigations grew in intensity, several high-ranking officials at the CDC and FDA were forced to step down and withdraw from government.”
  • “Nearing the end of 2027, reports of new neurological symptoms began to emerge.”
  • “Several parents claimed that their children were experiencing neurological symptoms.”
  • “Small groups of individuals spread throughout the country, for example, who felt that natural cures such as garlic and vitamins would be more effective at treating SPARS than an “untested” drug, were much less likely to accept Kalocivir as a treatment option or even seek medical attention for SPARS-like symptoms. Similarly, some ethnic minorities, and particularly ethnic groups who lived close together in large, tight-knit communities, also rejected Kalocivir.”
  • “As the pandemic tapered off, several influential politicians and agency representatives came under fire for sensationalizing the severity of the event for perceived political gain. As with many public health interventions, successful efforts to reduce the impact of the pandemic created the illusion that the event was not nearly as serious as experts suggested it would be. President Archer’s detractors in the Republican Party seized the opportunity to publicly disparage the President and his administration’s response to the pandemic, urging voters to elect “a strong leader with the best interests of the American people at heart.” “
  • “In an effort to further reach certain population subgroups, agency officials enlisted the help of well-known scientists, celebrities, and government officials to make short videos and Zap clips and, in a few cases, give interviews to major media outlets. Among those chosen were former President Jaclyn Bennett; BZee, a popular hiphop star; and Paul Farmer, co-founder of Partners in Health and a renowned global health expert… While common messaging resulted in more cohesive traditional media coverage, the celebrity outreach campaign was more problematic.”
  • “What are the roles of a media-literate staff and organizational capacity to communicate via both social and traditional media platforms critical to understanding and influencing public debates about an MCM like Kalocivir?”
  • “What communication strategies might be effective for breaking into, and engaging with otherwise self-isolating groups who oppose a recommended MCM like Corovax and might be placing themselves and others at risk during the outbreak?”
  • How might federal health authorities avoid people possibly seeing an expedited SPARS vaccine development and testing process as somehow “rushed” and inherently flawed, even though that process still meets the same safety and efficacy standards as any other vaccine?
  • “That month, a group of parents whose children developed mental retardation as a result of encephalitis in the wake of Corovax vaccination sued the federal government, demanding removal of the liability shield protecting the pharmaceutical companies responsible for developing and manufacturing Corovax.”
  • “Given the positive reaction to the federal government’s response and the fact that the majority of US citizens willing to be vaccinated had already been immunized, the negative publicity surrounding adverse reactions had little effect on nationwide vaccination rates.”
  • “A widespread social media movement led primarily by outspoken parents of affected children, coupled with widespread distrust of “big pharma,” supported the narrative that the development of SPARS MCMs was unnecessary and driven by a few profit-seeking individuals. Conspiracy theories also proliferated across social media, suggesting that the virus had been purposely created and introduced to the population by drug companies or that it had escaped from a government lab secretly testing bioweapons.”
  • “In order to prioritize distribution of limited Corovax supply, the federal government requested that states report summary information for patient electronic health records (EHRs) to estimate the number of individuals in high-risk populations. This effort was met with resistance from the public, who protested the federal government accessing their private medical information.”
  • “The Corovax vaccination program met resistance from several groups: alternative medicine proponents, Muslims, African Americans, and anti-vaccination activists. Initially operating independently, these groups banded together via social media to increase their influence.”
  • “Japan announced that it would not approve Corovax for use in Japan in favor of developing and producing its own vaccine.”

Washington University: Covid Finds New Ways To Infect Humans!

via Thailand Medical News

Coronavirus News: More good news as Scientists from Washington University School of Medicine in St. Louis have now discovered that the SARS-CoV-2 coronavirus is evolving even faster and is now developing its own strategies to infect human host cells no longer through the ACE2 receptors but by other receptors and means! It is doing so by causing a variety of mutations involving amino acid bases at position 484 of the spike protein.

This new study warns that current antibody-based therapeutics and vaccines might actually end up no longer being effective. Already numerous variants of concerns or VOCs and variants of interest or VOIs are found to be possessing mutations such as the E484K on them and to date most researchers do not really know the true significance of this mutation. It is only a matter of time (If it has not already occurred and it is just mankind is still too slow in catching up via genomic surveillance) that an even more potent mutation has occurred at this position before the virus totally does not need to rely on any ACE2 receptors for viral entry.

In screening for new models of SARS-CoV-2 infection, the study team identified human H522 lung adenocarcinoma cells as naturally permissive to SARS-CoV-2 infection despite complete absence of ACE2 expression. Remarkably, H522 infection requires the E484D S variant; viruses expressing wild-type S are not infectious. Anti-S monoclonal antibodies differentially neutralize SARS-CoV-2 E484D S in H522 cells as compared to ACE2-expressing cells. Sera from vaccinated individuals did block this alternative entry mechanism, whereas convalescent sera was less effective. Though the H522 receptor remains unknown, depletion of surface heparan sulfates block H522 infection. Temporally resolved transcriptomic and proteomic profiling reveal alterations in cell cycle and the antiviral host cell response, including MDA5-dependent activation of type-I interferon signaling.

Importantly these findings establish an alternative SARS-CoV-2 host cell receptor for the E484D SARS-CoV-2 variant, which may impact tropism of SARS-CoV-2 and consequently human disease pathogenesis.

The study findings were published on the peer reviewed journal: Cell Reports by Elsevier Group.

Initially in the COVID-19 outbreak, researchers identified how SARS-CoV-2 coronavirus gets inside cells to cause infection. All current COVID-19 vaccines and antibody-based therapeutics were designed to disrupt this route into cells, which requires a receptor called ACE2.

Alarmingly the study team has now found that a single mutation gives SARS-CoV-2 the ability to enter cells through another route ie one that does not require ACE2.

Importantly, the ability to use an alternative entry pathway opens up the possibility of evading COVID-19 antibodies or vaccines.

Most significantly the study findings indicate that the virus can change in unexpected ways and find new ways to cause infection.

Co-senior author Dr Sebla Kutluay, PhD, an assistant professor of molecular microbiology at Washington University told Thailand Medical News, “This mutation occurred at one of the spots that changes a lot as the virus circulates in the human population. Most of the time, alternative receptors and attachment factors simply enhance ACE2-dependent entry. But in this case, we have discovered an alternative way to infect a key cell type-a human lung cell and that the virus acquired this ability via a mutation that we know arises in the population. This is something we definitely need to know more about.”

This new alarming finding was serendipitous. Last year, Dr Kutluay and co-senior author Dr M. Ben Major, PhD, the Alan A. and Edith L. Wolff Distinguished Professor of Cell Biology & Physiology, planned to study the molecular changes that occur inside cells infected with SARS-CoV-2.

Typically most researchers study SARS-CoV-2 in primate kidney cells because the virus grows well in them, but Dr Kutluay and Dr Major felt it was important to do the study in lung or other cells similar to the ones that are naturally infected.

In order to find more relevant cells capable of growing SARS-CoV-2, Dr Kutluay and Dr Major screened a panel of 10 lung and head-and-neck cell lines.

Dr Major added, “The only one that was able to be infected was the one I had included as a negative control. It was a human lung cancer cell line with no detectable ACE2. So that was a crazy surprise.”

Dr Kutluay, Dr Major and the rest of the study team including co-first authors and postdoctoral researchers Dr Maritza Puray-Chavez, PhD, and Dr Kyle LaPak, PhD, as well as co-authors Dr Dennis Goldfarb, PhD, an assistant professor of cell biology & physiology and of medicine, and Dr Steven L. Brody, MD, the Dorothy R. and Hubert C. Moog Professor of Pulmonary Diseases in Medicine, and a professor of radiology, discovered that the virus they were using for experiments had picked up a mutation.

This virus had originally been obtained from a person in Washington State with COVID-19, but as it was grown over time in the laboratory, it had acquired a mutation that led to a change of a single amino acid at position 484 in the virus’s spike protein.

The SARS-CoV-2 coronavirus uses spike to attach to ACE2, and position 484 is a hot spot for mutations. A variety of mutations at the same position have been found in viral variants from people and mice, and in virus grown in the lab.

Interestingly some of the mutations found in virus samples taken from people are identical to the one Dr Kutluay and Dr Major found in their variant. The Alpha and Beta variants of concern have mutations at position 484, although those mutations are different.

Dr Major warned, “This position is evolving over time within the human population and in the lab. Given our data and those of others, it is possible that the virus is under selective pressure to get into cells without using ACE2. In so many ways, it is scary to think of the world’s population fighting a virus that is diversifying the mechanisms by which it can infect cells.”

In order to determine whether the ability to use an alternative entry pathway allowed the virus to escape COVID-19 antibodies or vaccines, the study team screened panels of antibodies and blood serum with antibodies from individuals who have been vaccinated for COVID-19 or recovered from COVID-19 infection. There was some variation, but in general, the antibodies and blood sera were only slightly effective against the virus with the mutation.

It should be noted that it is not yet clear whether the alternative pathway comes into play under real-world conditions when individuals are infected with SARS-CoV-2. Before the study team can begin to address that question, they must first find the alternative receptor that the virus is using to get into cells.

Dr Kutluay added, “It is possible that the virus uses ACE2 until it runs out of cells with ACE2, and then it switches over to using this alternative pathway. This might have relevance in the body, but without knowing the receptor, we cannot say what the relevance is going to be.”

Dr Major added, “That’s where we’re going right now. What is the receptor? If it’s not ACE2, what is it?”